Archive for the ‘Uncategorized’ Category

The Group of 300 Who Rule the World. Fact or Conspiracy Theory of Dr. John Coleman, MI6. 2023-06-12. Jorma A Jyrkkanen, BSc, PDP

June 12, 2023

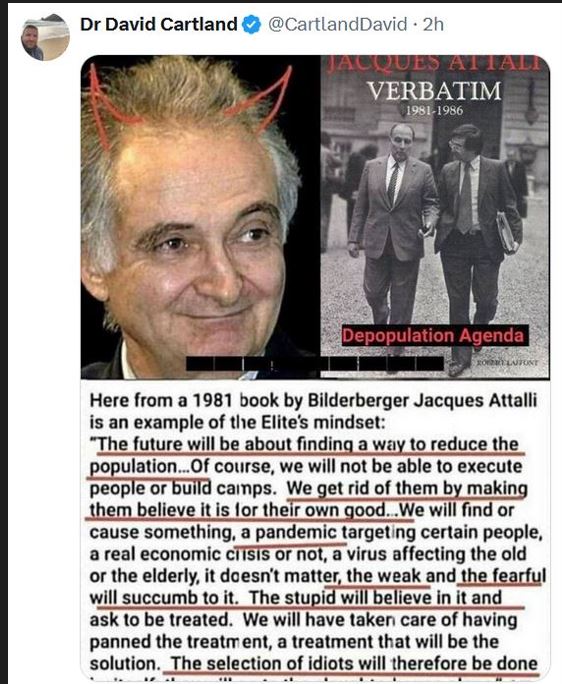
THE ALLEGATIONS ARE CITED BELOW. ONE CANNOT BUT SHOCKINGLY NOTICE AND COMPARE THE EVENTS SURROUNDING THE COVID ROLL OUT AND HOW MARVELOUSLY THEY FIT THE STATED OBJECTIVES OF ONE JACQUES ATTILLI A BILDERBERGER.

GLOBALISTS PLANS AN EARLY WARNING
MI6 EXPOSE ON G300. Dr John Coleman

Who Are They

PAST AND PRESENT MEMBERS OF THE COMMITTEE OF 300:

Abergavemy, Marquis of. Acheson, Dean. Adeane, Lord Michael. Agnelli, Giovanni. Alba, Duke of. Aldington, Lord. Aleman, Miguel. Allihone, Professor T. E. Alsop Family Designate. Amory, Houghton. Anderson, Charles A. Anderson, Robert 0. Andreas, Dwayne. Asquith, Lord. Astor, John Jacob and successor, Waldorf. Aurangzeb, Descendants of. Austin, Paul. Baco, Sir Ranulph BalFour, Arthur. Balogh, Lord. Bancroft, Baron Stormont. Baring. Barnato, B. Barran, Sir John. Baxendell, Sir Peter. Beatrice of Savoy, Princess. Beaverbrook, Lord. Beck, Robert. Beeley, Sir Harold. Beit, Alfred. Benn, Anthony Wedgewood. Bennet, John W. Benneton, Gilberto or alternate Carlo. Bertie, Andrew. Besant, Sir Walter. Bethal, Lord Nicholas. Bialkin, David. Biao, Keng. Bingham, William. Binny, J. F. Blunt, Wilfred. Bonacassi, Franco Orsini. Bottcher, Fritz. Bradshaw, Thornton. Brandt, Willy. Brewster, Kingman. Buchan, Alastair. Buffet, Warren. Bullitt, William C. Bulwer-Lytton, Edward. Bundy, McGeorge. Bundy, William. Bush, George. Cabot, John. Family Designate. Caccia, Baron Harold Anthony. Cadman, Sir John. Califano, Joseph. Carrington, Lord. Carter, Edward. Catlin, Donat. Catto, Lord. Cavendish, Victor C. W. Duke of Devonshire. Chamberlain, Houston Stewart. Chang, V. F. Chechirin, Georgi or Family Designate. Churchill, Winston. Cicireni, V. or Family Designate. Cini, Count Vittorio. Clark, Howard. Cleveland, Amory. Cleveland, Harland. Clifford, Clark. Cobold, Lord. Coffin, the Rev William Sloane. Constanti, House of Orange. Cooper, John. Family Designate. Coudenhove- Kalergi, Count. Cowdray, Lord. Cox, Sir Percy. Cromer, Lord Evelyn Baring. Crowther, Sir Eric. Cumming, Sir Mansfield. Curtis, Lionel. d’Arcy, William K. D’Avignon, Count Etienne. Danner, Jean Duroc. Davis, John W. de Benneditti, Carlo. De Bruyne, Dirk. De Gunzberg, Baron Alain. De Lamater, Major General Walter. De Menil, Jean. De Vries, Rimmer. de Zulueta, Sir Philip. de’Aremberg, Marquis Charles Louis. Delano. Family Designate. Dent, R. Deterding, Sir Henri. di Spadaforas, Count Guitierez, (House Douglas-Home, Sir Alec. Drake, Sir Eric. Duchene, Francois. DuPont. Edward, Duke of Kent. Eisenberg, Shaul. Elliott, Nicholas. Elliott, William Yandel. Elsworthy, Lord. Farmer, Victor. Forbes, John M. Foscaro, Pierre. France, Sir Arnold. Fraser, Sir Hugh. Frederik IX, King of Denmark Family Designate. Freres, Lazard. Frescobaldi, Lamberto. Fribourg, Michael. Gabor, Dennis. Gallatin, Albert. Family Designate. Gardner, Richard. Geddes, Sir Auckland. Geddes, Sir Reay. George, Lloyd. Giffen, James. Gilmer, John D. Giustiniani, Justin. Gladstone, Lord. Gloucestor, The Duke of. Gordon, Walter Lockhart. Grace, Peter J. Greenhill, Lord Dennis Arthur. Greenhill, Sir Dennis. Grey, Sir Edward. Gyllenhammar, Pierres. Haakon, King of Norway. Haig, Sir Douglas. Hailsham, Lord. Haldane, Richard Burdone. Halifax, Lord. Hall, Sir Peter Vickers. Hambro, Sir Jocelyn. Hamilton, Cyril. Harriman, Averill. Hart, Sir Robert. Hartman, Arthur H. Healey, Dennis. Helsby, Lord. Her Majesty Queen Elizabeth II. Her Majesty Queen Juliana. Her Royal Highness Princess Beatrix. Her Royal Highness Queen Margreta. Heseltine, Sir William. Hesse, Grand Duke descendants, Family Designate. Hoffman, Paul G. Holland, William. House of Braganza. House of Hohenzollern. House, Colonel Mandel. Howe, Sir Geoffrey. Hughes, Thomas H. Hugo, Thieman. Hutchins, Robert M. Huxley, Aldous. Inchcape, Lord. Jamieson, Ken. Japhet, Ernst Israel. Jay, John. Family Designate. Keynes, John Maynard. Jodry, J. J. Joseph, Sir Keith. Katz, Milton. Kaufman, Asher. Keith, Sir Kenneth. Keswick, Sir William Johnston, or Keswick, H.N.L. Keswick, William Johnston. Kimberly, Lord. King, Dr. Alexander. Kirk, Grayson L. Kissinger, Henry. Kitchener, Lord Horatio. Kohnstamm, Max. Korsch, Karl. Lambert, Baron Pierre. Lawrence, G. Lazar. Lehrman, Lewis. Lever, Sir Harold. Lewin, Dr. Kurt. Lippmann, Walter. Livingstone, Robert R. Family Designate. Lockhart, Bruce. Lockhart, Gordon. Linowitz, S. Loudon, Sir John. Luzzatto, Pieipaolo. Mackay, Lord, of Clasfern. Mackay- Tallack, Sir Hugh. Mackinder, Halford. MacMillan, Harold. Matheson, Jardine. Mazzini, Gueseppi. McClaughlin, W. E. McCloy, John J. McFadyean, Sir Andrew. McGhee, George. McMillan, Harold. Mellon, Andrew. Mellon, William Larimer or Family Designate. Meyer, Frank. Michener, Roland. Mikovan, Anastas. Milner, Lord Alfred. Mitterand, Francois. Monett, Jean. Montague, Samuel. Montefiore, Lord Sebag or Bishop Hugh. Morgan, John P. Mott, Stewart. Mountain, Sir Brian Edward. Mountain, Sir Dennis. Mountbatten, Lord Louis. Munthe, A., or family designate. Naisbitt, John. Neeman, Yuval. Newbigging, David. Nicols, Lord Nicholas of Bethal. Norman, Montague. O’Brien of Lotherby, Lord. Ogilvie, Angus. Okita, Saburo. Oldfield, Sir Morris. Oppenheimer, Sir Earnest, and successor, Harry. Ormsby Gore, David (Lord Harlech). Orsini, Franco Bonacassi. Ortolani. Umberto. Ostiguy, J.P.W. Paley, William S. Pallavacini. Palme, Olaf. Palmerston. Palmstierna, Jacob. Pao, Y.K. Pease, Richard T. Peccei, Aurellio. Peek, Sir Edmund. Pellegreno, Michael, Cardinal. Perkins, Nelson. Pestel, Eduard. Peterson, Rudolph. Petterson, Peter G. Petty, John R. Philip, Prince, Duke of Edinburgh. Piercy, George. Pinchott, Gifford. Pratt, Charles. Price Waterhouse, Designate. Radziwall. Ranier, Prince. Raskob, John Jacob. Recanati. Rees, John Rawlings. Rees, John. Rennie, Sir John. Rettinger, Joseph. Rhodes, Cecil John. Rockefeller, David. Role, Lord Eric of Ipsden. Rosenthal, Morton. Rostow, Eugene. Rothmere, Lord. Rothschild Elie de or Edmon de and/or Baron RothschiLd Runcie, Dr.Robert. Russell, Lord John. Russell, Sir Bertrand. Saint Gouers, Jean. Salisbury, Marquisse de Robert Gascoiugne Cecil. Shelburne, The Salisbury, Lord. Samuel, Sir Marcus. Sandberg, M. G. Sarnoff, Robert. Schmidheiny, Stephan or alternate brothers Thomas, Alexander. Schoenberg, Andrew. Schroeder. Schultz, George. Schwartzenburg, E. Shawcross, Sir Hartley. Sheridan, Walter. Shiloach, Rubin. Silitoe, Sir Percy. Simon, William. Sloan, Alfred P. Smuts, Jan. Spelman. Sproull, Robert. Stals, Dr. C. Stamp, Lord Family designate. Steel, David. Stiger, George. Strathmore, Lord. Strong, Sir Kenneth. Strong, Maurice. Sutherland. Swathling, Lord. Swire, J. K. Tasse, G. Or Family Designate. Temple, Sir R. Thompson, William Boyce. Thompson, Lord. Thyssen- Bornamisza, Baron Hans Henrich. Trevelyn, Lord Humphrey. Turner, Sir Mark. Turner, Ted. Tyron, Lord. Urquidi, Victor. Van Den Broek, H. Vanderbilt. Vance, Cyrus. Verity, William C. Vesty, Lord Amuel. Vickers, Sir Geoffrey. Villiers, Gerald Hyde family alternate. Volpi, Count. von Finck, Baron August. von Hapsburg, Archduke Otto, House of Hapsburg-Lorraine. Von Thurn and Taxis, Max. Wallenberg, Peter or Family Designate. Wang, Kwan Cheng, Dr. Warburg, S. C. Ward Jackson, Lady Barbara. Warner, Rawleigh. Warnke, Paul. Warren, Earl. Watson, Thomas. Webb, Sydney. Weill, David. Weill, Dr. Andrew. Weinberger, Sir Caspar. Weizman, Chaim. Wells, H. G. Wheetman, Pearson (Lord Cowdray). White, Sir Dick Goldsmith. Whitney, Straight. Wiseman, Sir William. Wittelsbach. Wolfson, Sir Isaac. Wood, Charles. Young, Owen. The Club of Rome, the Venetian Black Nobility, the Royal Institute for International Affairs (RIIA), the Council on Foreign Relations (CFR), the Bilderbergers, Trilaterals, the Zionists, Freemasonry, the Illuminati, the Order of St. John of Jerusalem. Read the Book.

WHAT DO THEY WANT?

RULERS OF OUR WORLD: The Committee of 300 is a small group of insidious people who control all aspects of our world. Through MI6 they ordered the murder of President Lincoln and President Kennedy. AIDS was created and WHO injected it into millions through the Smallpox vaccines. THEIR GOALS: (1) A One World Government with a unified church and monetary system under their direction. (2) The utter destruction of all national identity and national pride. (3) The destruction of religion and more especially the Christian religion, with the one exception, their own creation mentioned above. (4) Control of each and every person through means of mind control and nanotechnology which would create human-like robots and a system of terror. (5) An end to all industrialization and the production of nuclear generated electric power in what they call “the post-industrial zero-growth society.” (6) Legalization of drugs and pornography. (7) Depopulation of large cities. (8) Suppression of all scientific development except for those deemed beneficial by the Committee. Especially targeted is nuclear energy for peaceful purposes. (9) Cause by means of limited wars in the advanced countries, and by means of starvation and diseases in Third World countries, the death of 3 billion people by the year 2050, people they call “useless eaters.” (10) To weaken the moral fiber of the nation and to demoralize workers in the labor class by creating mass unemployment. (11) To keep people everywhere from deciding their own destinies by means of one created crisis after another and then “managing” such crises. (12) To introduce new cults. (13) To cause a total collapse of the world’s economies and engender total political chaos. (14) To take control of all Foreign and domestic policies of the United States. (15) Give full support to supranational institutions such as the United Nations (UN), the World Health Organization (WHO), the International Monetary Fund (IMF), the Bank of International Settlements (BIS) and the World Economic Forum(WEF) and the World Court. (16) Penetrate and subvert all governments, and work from within them to destroy the sovereign integrity of nations represented by them. (17) Organize a world-wide terrorist apparatus and negotiate with terrorists whenever terrorist activities take place. (18) Take control of education in America with the intent and purpose of utterly and completely destroying it.

DUTCH BANKER CLAIMS THEY ARE INVOLVED IN PEDOPHILIA AND CHILD TRAFFICKING AND MURDER

President Dwight D Eisenhower’s Farewell Speech Warning of the Power Grab Potential of a Unified Military Industrial Complex and the Threat it Poses to Democracy and the Constitution

Until the latest of our world conflicts, the United States had no armaments industry. American makers of plowshares could, with time and as required, make swords as well. But now we can no longer risk emergency improvisation of national defense; we have been compelled to create a permanent armaments industry of vast proportions. Added to this, three and a half million men and women are directly engaged in the defense establishment. We annually spend on military security more than the net income of all United State corporations.

This conjunction of an immense military establishment and a large arms industry is new in the American experience. The total influence-economic, political, even spiritual-is felt in every city, every state house, every office of the Federal government. We recognize the imperative need for this development. Yet we must not fail to comprehend its grave implications. Our toil, resources and livelihood are all involved; so is the very structure of our society.

In the councils of government, we must guard against the acquisition of unwarranted influence, whether sought or unsought, by the military-industrial complex. The potential for the disastrous rise of misplaced power exists and will persist.

We must never let the weight of this combination endanger our liberties or democratic processes. We should take nothing for granted only an alert and knowledgeable citizenry can compel the proper meshing of the huge industrial and military machinery of defense with our peaceful methods and goals, so that security and liberty may prosper together. [CIA+FBI+SPECIAL EXECUTIVE SERVICES+MIC+WEF+Bilderberg+need Constitutional Oversight in this regard]

Akin to, and largely responsible for the sweeping changes in our industrial-military posture, has been the technological revolution during recent decades.

In this revolution, research has become central; it also becomes more formalized, complex, and costly. A steadily increasing share is conducted for, by, or at the direction of, the Federal government.

Today, the solitary inventor, tinkering in his shop, has been over shadowed by task forces of scientists in laboratories and testing fields. In the same fashion, the free university, historically the fountainhead of free ideas and scientific discovery, has experienced a revolution in the conduct of research. Partly because of the huge costs involved, a government contract becomes virtually a substitute for intellectual curiosity. For every old blackboard there are now hundreds of new electronic computers.

The prospect of domination of the nation’s scholars by Federal employment, project allocations, and the power of money is ever present and is gravely to be regarded.

Yet, in holding scientific research and discovery in respect, as we should, we must also be alert to the equal and opposite danger that public policy could itself become the captive of a scientific-technological elite.

It is the task of statesmanship to mold, to balance, and to integrate these and other forces, new and old, within the principles of our democratic system-ever aiming toward the supreme goals of our free society.

******

Another factor in maintaining balance involves the element of time. As we peer into society’s future, we-you and I, and our government-must avoid the impulse to live only for today, plundering, for our own ease and convenience, the precious resources of tomorrow. We cannot mortgage the material assets of our grandchildren without risking the loss also of their political and spiritual heritage. We want democracy to survive for all generations to come, not to become the insolvent phantom of tomorrow.

******

Down the long lane of the history yet to be written America knows that this world of ours, ever growing smaller, must avoid becoming a community of dreadful fear and hate, and be, instead, a proud confederation of mutual trust and respect.

Such a confederation must be one of equals. The weakest must come to the conference table with the same confidence as do we, protected as we are by our moral, economic, and military strength. That table, though scarred by many past frustrations, cannot be abandoned for the certain agony of the battlefield.

Disarmament, with mutual honor and confidence, is a continuing imperative. Together we must learn how to compose difference, not with arms, but with intellect and decent purpose. Because this need is so sharp and apparent I confess that I lay down my official responsibilities in this field with a definite sense of disappointment. As one who has witnessed the horror and the lingering sadness of war-as one who knows that another war could utterly destroy this civilization which has been so slowly and painfully built over thousands of years-I wish I could say tonight that a lasting peace is in sight.

Happily, I can say that war has been avoided. Steady progress toward our ultimate goal has been made. But, so much remains to be done. As a private citizen, I shall never cease to do what little I can to help the world advance along that road.

DR.COLEMAN UK SS

THE COMMITTEE OF 300: The destruction and control of America and the World. The depopulation of millions of innocent people. The public execution of President John F. Kennedy. The control of U.S. Elections and elections around the world. The release of AIDS and deadly viruses. This is the work of the insidious Committee of 300. How long will America and humanity allow them to continue this rule of corruption, death and destruction? They will not give up their power. It must be forcibly removed from them. They are moving forward with the following agenda unless we stop them.

The Intent and Purpose of the Committee of 300 is to Bring to Pass the Following Conditions: A One World Government and one-unit monetary system under permanent non-elected hereditary Oligarch’s who self select from among their numbers in the form of a feudal system as it was in the Middle Ages. In this One World entity, population will be limited by restrictions on the number of children per family, diseases, wars, famines, until 1 billion people who are useful to the ruling class, in areas which will be strictly and clearly defined, remain as the total world population. There will be no middle class, only rulers and servants. All laws will be uniform under a legal system of world courts practicing the same unified code of laws, backed up by a One World Government police force and a One World unified military to enforce laws in all former countries where no national boundaries shall exist. The system will be on the basis of a welfare state; those who are obedient and subservient to the One World Government will be rewarded with the means to live; those who are rebellious will simply be starved to death or be declared outlaws, thus a target for anyone who wishes to kill them. Privately owned firearms or weapons of any kind will be prohibited. Only one religion will be allowed and that will be in the form of a One World Government Church, which has been in existence since 1920 as we shall see. Satanism, Luciferianism and Witchcraft shall he recognized as legitimate One World Government curricula with no private or church schools. All Christian churches have already been subverted and Christianity will be a thing of the past in the One World Government. To induce a state where there is no individual freedom or any concept of liberty surviving, there shall be no such thing as republicanism, sovereignty or rights residing with the people. National pride and racial identity shall be stamped out and in the transition phase it shall be subject to the severest penalties to even mention one’s racial origin. Each person shall be fully indoctrinated that he or she is a creature of the One World Government with an identification number clearly marked on their person so as to be readily accessible, which identifying number shall be in the master file of the NATO computer in Brussels, Belgium, subject to instant retrieval by any agency of the One World Government at any time. The master Files of the CIA, FBI, state and local police agencies, IRS, FEMA, Social Security shall be vastly expanded and form the basis of personal records of all individuals in the United States. Marriage shall be outlawed and there shall be no family life as we know it. Children will be removed from their parents at an early-age and brought up by wards as state property. Such an experiment was carried out in East Germany under Erich Honnecker when children were take away from parents considered by the state to be disloyal citizens. Women will be degraded through the continued process of “women’s liberation” movements. Free sex shall be mandatory. Failure to comply at least once by the age of 20 shall be punishable by severe reprisals against her person. Self-abortion shall be taught and practiced after two children are born to a woman; such records shall be contained in the personal file of each woman in the One World Government’s regional computers. If a woman falls pregnant after she has previously given birth to two children, she shall be forcibly removed to an abortion clinic for such an abortion and sterilization to be carried out. Pornography shall be promoted and be compulsory showing in every theater of cinema, including homosexual and lesbian pornography. The use of “recreational” drugs shall be compulsory, with each person allotted drug quotas which can be purchased at One World Government stores throughout the world. Mind control drugs will be expanded and usage become compulsory. Such mind control drugs shall be given in food and/or water supplies without the knowledge and/or consent of the people. Drug bars shall be set up, run by One World Government employees, where the slave-class shall be able to spend their free time. In this manner the non-elite masses will be reduced to the level and behavior of controlled animals with no will of their own and easily regimented and controlled. The economic system shall be based upon the ruling oligarchical class allowing just enough foods and services to be produced to keep the mass slave labor camps going. All wealth shall be aggregated in the hands of the elite members of the Committee of 300. Each individual shall be indoctrinated to understand that he or she is totally dependent upon the state for survival. The world shall be ruled by Committee of 300 Executive Decrees which become instant law. Courts of punishment and not courts of justice shall exist. Industry is to be totally destroyed along with nuclear powered energy systems. Only the Committee of 300 members and their elitists shall have the right to any of the earth’s resources. Agriculture shall be solely in the hands of the Committee of 300 with food production strictly controlled. As these measures begin to take effect, large populations in the cities shall be forcibly removed to remote areas and those who refuse to go shall be exterminated in the manner of the One World Government experiment carried out by Pol Pot in Cambodia. Euthanasia for the terminally ill and the aged shall be compulsory. No cities shall be larger than a predetermined number as described in the work of Kalgeri. Essential workers will be moved to other cities if the one they are in becomes overpopulated. Other non-essential workers will be chosen at random and sent to underpopulated cities to fill “quotas.” At least 4 billion “useless eaters” shall be eliminated by the year 2050 by means of limited wars, organized epidemics of fatal rapid-acting diseases and starvation. Energy, food and water shall be kept at subsistence levels for the non-elite, starting with the White populations of Western Europe and North America and then spreading to other races. The population of Canada, Western Europe and the United States will be decimated more rapidly than on other continents, until the world’s population reaches a manageable level of 1 billion, of which 500 million will consist of Chinese and Japanese races, selected because they are people who have been regimented for centuries and who are accustomed to obeying authority without question. From time to time there shall be artificially contrived food and water shortages and medical care to remind the masses that their very existence depends on the goodwill of the Committee of 300. After the destruction of housing, auto, steel and heavy goods industries, there shall he limited housing, and industries of any kind allowed to remain shall be under the direction of NATO’s Club of Rome as shall all scientific and space exploration development, limited to the elite under the control of the Committee of 300. Space weapons of all former nations shall be destroyed along with nuclear weapons. All essential and non-essential pharmaceutical products, doctors, dentists and health care workers will be registered in the central computer data bank and no medicine or medical care will he prescribed without express permission of regional controllers responsible for each city, town and village. The United States will be flooded by peoples of alien cultures who will eventually overwhelm America, people with no concept of what the United States Constitution stands for and who will, in consequence, do nothing to defend it, and in whose minds the concept of liberty and justice is so weak as to matter little. Food and shelter shall be the main concern. No central bank save the Bank of International Settlement and the World Bank shall be allowed to operate. Private banks will be outlawed. Remuneration for work performed shall be under a uniform predetermined scale throughout the One World Government. There shall be no wage disputes allowed, nor any diversion from the standard uniform scales of pay laid down by the One World Government. Those who break the law will be instantly executed. There shall be no cash or coinage in the hands of the non- elite. All transactions shall be carried out by means of digital currency which shall bear the identification number of the holder. Any person who in any way infringes the rules and regulations of the Committee of 300 shall have the use of his or her digital currency suspended for varying times according to the nature and severity of the infringement. Such persons will find, when they go to make purchases, that their digital currency is blacklisted and they will not be able to obtain services of any kind. Attempts to trade “old” coins, that is to say silver coins of previous and now defunct nations, shall be treated as a capital crime subject to the death penalty. All such coinage shall be required to be surrendered within a given time along with guns, rifles, explosives and automobiles. Only the elite and One World Government high-ranking functionaries will be allowed private transport, weapons, coinage and automobiles. If the offense is a serious one, the digital currency will be shut off at the checking point where it is presented. Thereafter that person shall not be able to obtain food, water, shelter and employment medical services, and shall be officially listed as an outlaw. Large bands of outlaws will thus be created and they will live in regions that best afford subsistence, subject to being hunted down and shot on sight. Persons assisting outlaws in any way whatsoever, shall likewise be shot. Outlaws who fail to surrender to the police or military after a declared period of time, shall have a former family member selected at random to serve prison terms in their stead. Rival factions and groups such as Arabs and Jews and African tribes shall have differences magnified and allowed to wage wars of extermination against each other under the eyes of NATO and U.N. observers. The same tactics will be used in Central and South America. These wars of attrition shall take place before the take-over of the One World Government and shall be engineered on every continent where large groups of people with ethnic and religious differences live, such as the Sikhs, Moslem Pakistanis and the Hindu Indians. Ethnic and religious differences shall be magnified and exacerbated and violent conflict as a means of “settling” their differences shall be encouraged and fostered. All information services and print media shall be under the control of the One World Government. Regular brainwashing control measures shall be passed off as “entertainment” in the manner in which it was practiced and became a fine art in the United States. Youths removed from “disloyal parents,” shall receive special education designed to brutalize them. Youth of both sexes shall receive training to qualify as prison guards for the One World labor camp system. The above was written in 1991 by Dr. John Coleman. Dr. John Coleman was an Intelligence Officer for over 45 years and his book of truth is based on 20 years of relentless research. We can already see many of these things happening today. The Committee of 300 has already penetrated and subverted all governments through the World Economic Forum and United Nations to destroy the sovereign integrity of the nations represented by them. The Committee of 300 has already taken control of the education system in America with the intent and purpose of utterly and completely destroying it. They have now targeted our innocent children through homosexuality, transgenderism and pedophilia. They operate and control the world’s Pedophile systems. The Committee of 300 must come to its swift end. They are in control of America right now and are the ones who orchestrated the fraudulent 2020 Election and put corrupt Biden in the White House. They will not allow Trump or Kennedy to be President of the United States. We must do what must be done. We must end the Committee of 300 once and for all for the sake of our innocent children and for the sake of all humanity. These are their names. These are the people that want to eliminate you and control you. These are the people who have been ruling our world for over 150 years through death and chaos inflicted upon billions of innocent people. These are the same people creating world wars for profits and deaths. These are the people behind engineered viruses and diseases that were released upon the world killing millions. These are the people that must be removed from our world. PAST AND PRESENT MEMBERS OF THE COMMITTEE OF 300 AS OF 1991: BILL GATES IS A NEW MEMBER Abergavemy, Marquis of. Acheson, Dean. Adeane, Lord Michael. Agnelli, Giovanni. Alba, Duke of. Aldington, Lord. Aleman, Miguel. Allihone, Professor T. E. Alsop Family Designate. Amory, Houghton. Anderson, Charles A. Anderson, Robert 0. Andreas, Dwayne. Asquith, Lord. Astor, John Jacob and successor, Waldorf. Aurangzeb, Descendants of. Austin, Paul. Baco, Sir Ranulph BalFour, Arthur. Balogh, Lord. Bancroft, Baron Stormont. Baring. Barnato, B. Barran, Sir John. Baxendell, Sir Peter. Beatrice of Savoy, Princess. Beaverbrook, Lord. Beck, Robert. Beeley, Sir Harold. Beit, Alfred. Benn, Anthony Wedgewood. Bennet, John W. Benneton, Gilberto or alternate Carlo. Bertie, Andrew. Besant, Sir Walter. Bethal, Lord Nicholas. Bialkin, David. Biao, Keng. Bingham, William. Binny, J. F. Blunt, Wilfred. Bonacassi, Franco Orsini. Bottcher, Fritz. Bradshaw, Thornton. Brandt, Willy. Brewster, Kingman. Buchan, Alastair. Buffet, Warren. Bullitt, William C. Bulwer-Lytton, Edward. Bundy, McGeorge. Bundy, William. Bush, George. Cabot, John. Family Designate. Caccia, Baron Harold Anthony. Cadman, Sir John. Califano, Joseph. Carrington, Lord. Carter, Edward. Catlin, Donat. Catto, Lord. Cavendish, Victor C. W. Duke of Devonshire. Chamberlain, Houston Stewart. Chang, V. F. Chechirin, Georgi or Family Designate. Churchill, Winston. Cicireni, V. or Family Designate. Cini, Count Vittorio. Clark, Howard. Cleveland, Amory. Cleveland, Harland. Clifford, Clark. Cobold, Lord. Coffin, the Rev William Sloane. Constanti, House of Orange. Cooper, John. Family Designate. Coudenhove-Kalergi, Count. Cowdray, Lord. Cox, Sir Percy. Cromer, Lord Evelyn Baring. Crowther, Sir Eric. Cumming, Sir Mansfield. Curtis, Lionel. d’Arcy, William K. D’Avignon, Count Etienne. Danner, Jean Duroc. Davis, John W. de Benneditti, Carlo. De Bruyne, Dirk. De Gunzberg, Baron Alain. De Lamater, Major General Walter. De Menil, Jean. De Vries, Rimmer. de Zulueta, Sir Philip. de’Aremberg, Marquis Charles Louis. Delano. Family Designate. Dent, R. Deterding, Sir Henri. di Spadaforas, Count Guitierez, (House Douglas-Home, Sir Alec. Drake, Sir Eric. Duchene, Francois. DuPont. Edward, Duke of Kent. Eisenberg, Shaul. Elliott, Nicholas. Elliott, William Yandel. Elsworthy, Lord. Farmer, Victor. Forbes, John M. Foscaro, Pierre. France, Sir Arnold. Fraser, Sir Hugh. Frederik IX, King of Denmark Family Designate. Freres, Lazard. Frescobaldi, Lamberto. Fribourg, Michael. Gabor, Dennis. Gallatin, Albert. Family Designate. Gardner, Richard. Gates, William Henry III Geddes, Sir Auckland. Geddes, Sir Reay. George, Lloyd. Giffen, James. Gilmer, John D. Giustiniani, Justin. Gladstone, Lord. Gloucestor, The Duke of. Gordon, Walter Lockhart. Grace, Peter J. Greenhill, Lord Dennis Arthur. Greenhill, Sir Dennis. Grey, Sir Edward. Gyllenhammar, Pierres. Haakon, King of Norway. Haig, Sir Douglas. Hailsham, Lord. Haldane, Richard Burdone. Halifax, Lord. Hall, Sir Peter Vickers. Hambro, Sir Jocelyn. Hamilton, Cyril. Harriman, Averill. Hart, Sir Robert. Hartman, Arthur H. Healey, Dennis. Helsby, Lord. Her Majesty Queen Elizabeth II. Her Majesty Queen Juliana. Her Royal Highness Princess Beatrix. Her Royal Highness Queen Margreta. Heseltine, Sir William. Hesse, Grand Duke descendants, Family Designate. Hoffman, Paul G. Holland, William. House of Braganza. House of Hohenzollern. House, Colonel Mandel. Howe, Sir Geoffrey. Hughes, Thomas H. Hugo, Thieman. Hutchins, Robert M. Huxley, Aldous. Inchcape, Lord. Jamieson, Ken. Japhet, Ernst Israel. Jay, John. Family Designate. Keynes, John Maynard. Jodry, J. J. Joseph, Sir Keith. Katz, Milton. Kaufman, Asher. Keith, Sir Kenneth. Keswick, Sir William Johnston, or Keswick, H.N.L. Keswick, William Johnston. Kimberly, Lord. King, Dr. Alexander. Kirk, Grayson L. Kissinger, Henry. Kitchener, Lord Horatio. Kohnstamm, Max. Korsch, Karl. Lambert, Baron Pierre. Lawrence, G. Lazar. Lehrman, Lewis. Lever, Sir Harold. Lewin, Dr. Kurt. Lippmann, Walter. Livingstone, Robert R. Family Designate. Lockhart, Bruce. Lockhart, Gordon. Linowitz, S. Loudon, Sir John. Luzzatto, Pieipaolo. Mackay, Lord, of Clasfern. Mackay-Tallack, Sir Hugh. Mackinder, Halford. MacMillan, Harold. Matheson, Jardine. Mazzini, Gueseppi. McClaughlin, W. E. McCloy, John J. McFadyean, Sir Andrew. McGhee, George. McMillan, Harold. Mellon, Andrew. Mellon, William Larimer or Family Designate. Meyer, Frank. Michener, Roland. Mikovan, Anastas. Milner, Lord Alfred. Mitterand, Francois. Monett, Jean. Montague, Samuel. Montefiore, Lord Sebag or Bishop Hugh. Morgan, John P. Mott, Stewart. Mountain, Sir Brian Edward. Mountain, Sir Dennis. Mountbatten, Lord Louis. Munthe, A., or family designate. Naisbitt, John. Neeman, Yuval. Newbigging, David. Nicols, Lord Nicholas of Bethal. Norman, Montague. O’Brien of Lotherby, Lord. Ogilvie, Angus. Okita, Saburo. Oldfield, Sir Morris. Oppenheimer, Sir Earnest, and successor, Harry. Ormsby Gore, David (Lord Harlech). Orsini, Franco Bonacassi. Ortolani. Umberto. Ostiguy, J.P.W. Paley, William S. Pallavacini. Palme, Olaf. Palmerston. Palmstierna, Jacob. Pao, Y.K. Pease, Richard T. Peccei, Aurellio. Peek, Sir Edmund. Pellegreno, Michael, Cardinal. Perkins, Nelson. Pestel, Eduard. Peterson, Rudolph. Petterson, Peter G. Petty, John R. Philip, Prince, Duke of Edinburgh. Piercy, George. Pinchott, Gifford. Pratt, Charles. Price Waterhouse, Designate. Radziwall. Ranier, Prince. Raskob, John Jacob. Recanati. Rees, John Rawlings. Rees, John. Rennie, Sir John. Rettinger, Joseph. Rhodes, Cecil John. Rockefeller, David. Role, Lord Eric of Ipsden. Rosenthal, Morton. Rostow, Eugene. Rothmere, Lord. Rothschild Elie de or Edmon de and/or Baron Rothschild Runcie, Dr. Robert. Russell, Lord John. Russell, Sir Bertrand. Saint Gouers, Jean. Salisbury, Marquisse de Robert Gascoiugne Cecil. Shelburne, The Salisbury, Lord. Samuel, Sir Marcus. Sandberg, M. G. Sarnoff, Robert. Schmidheiny, Stephan or alternate brothers Thomas, Alexander. Schoenberg, Andrew. Schroeder. Schultz, George. Schwartzenburg, E. Shawcross, Sir Hartley. Sheridan, Walter. Shiloach, Rubin. Silitoe, Sir Percy. Simon, William. Sloan, Alfred P. Smuts, Jan. Spelman. Sproull, Robert. Stals, Dr. C. Stamp, Lord Family designate. Steel, David. Stiger, George. Strathmore, Lord. Strong, Sir Kenneth. Strong, Maurice. Sutherland. Swathling, Lord. Swire, J. K. Tasse, G. Or Family Designate. Temple, Sir R. Thompson, William Boyce. Thompson, Lord. Thyssen-Bornamisza, Baron Hans Henrich. Trevelyn, Lord Humphrey. Turner, Sir Mark. Turner, Ted. Tyron, Lord. Urquidi, Victor. Van Den Broek, H. Vanderbilt. Vance, Cyrus. Verity, William C. Vesty, Lord Amuel. Vickers, Sir Geoffrey. Villiers, Gerald Hyde family alternate. Volpi, Count. von Finck, Baron August. von Hapsburg, Archduke Otto, House of Hapsburg-Lorraine. Von Thurn and Taxis, Max. Wallenberg, Peter or Family Designate. Wang, Kwan Cheng, Dr. Warburg, S. C. Ward Jackson, Lady Barbara. Warner, Rawleigh. Warnke, Paul. Warren, Earl. Watson, Thomas. Webb, Sydney. Weill, David. Weill, Dr. Andrew. Weinberger, Sir Caspar. Weizman, Chaim. Wells, H. G. Wheetman, Pearson (Lord Cowdray). White, Sir Dick Goldsmith. Whitney, Straight. Wiseman, Sir William. Wittelsbach. Wolfson, Sir Isaac. Wood, Charles. Young, Owen. Most Presidents and Prime Ministers around the world are controlled and were installed by the Committee of 300. There are thousands of people such as Klaus Schwab, leader of the World Economic Forum who work for the Committee of 300 to accomplish their will and purpose but are not direct members of the Committee of 300. They too must be removed from our society. The Committee of 300 also controls all the intelligence agencies such as MI6 and the CIA which are their most powerful tools to accomplish their goals worldwide. To restore America and humanity we must do away with the Committee of 300. This is the head of the snake that must be cut off. It will take a global effort of bravery and action. It must be done or we will lose America and the rest of the world to a future of global tyranny. They have already killed millions of innocent people and plan on killing billions more. They are coming after our children, they are sexualizing them and want to legalize Pedophilia. They will not stop unless we physically stop them by force. This is the reality of humanities fate. Criminals and mass murderers do not surrender their power. It must be taken from them for the sake of all humanity. They think they are gods themselves, the Olympians who have the right to decide who lives and who dies. They are gravely mistaken and their rule must come to a swift end.


Davos and WEF Forum

https://youtu.be/3Zs0sp36AGs

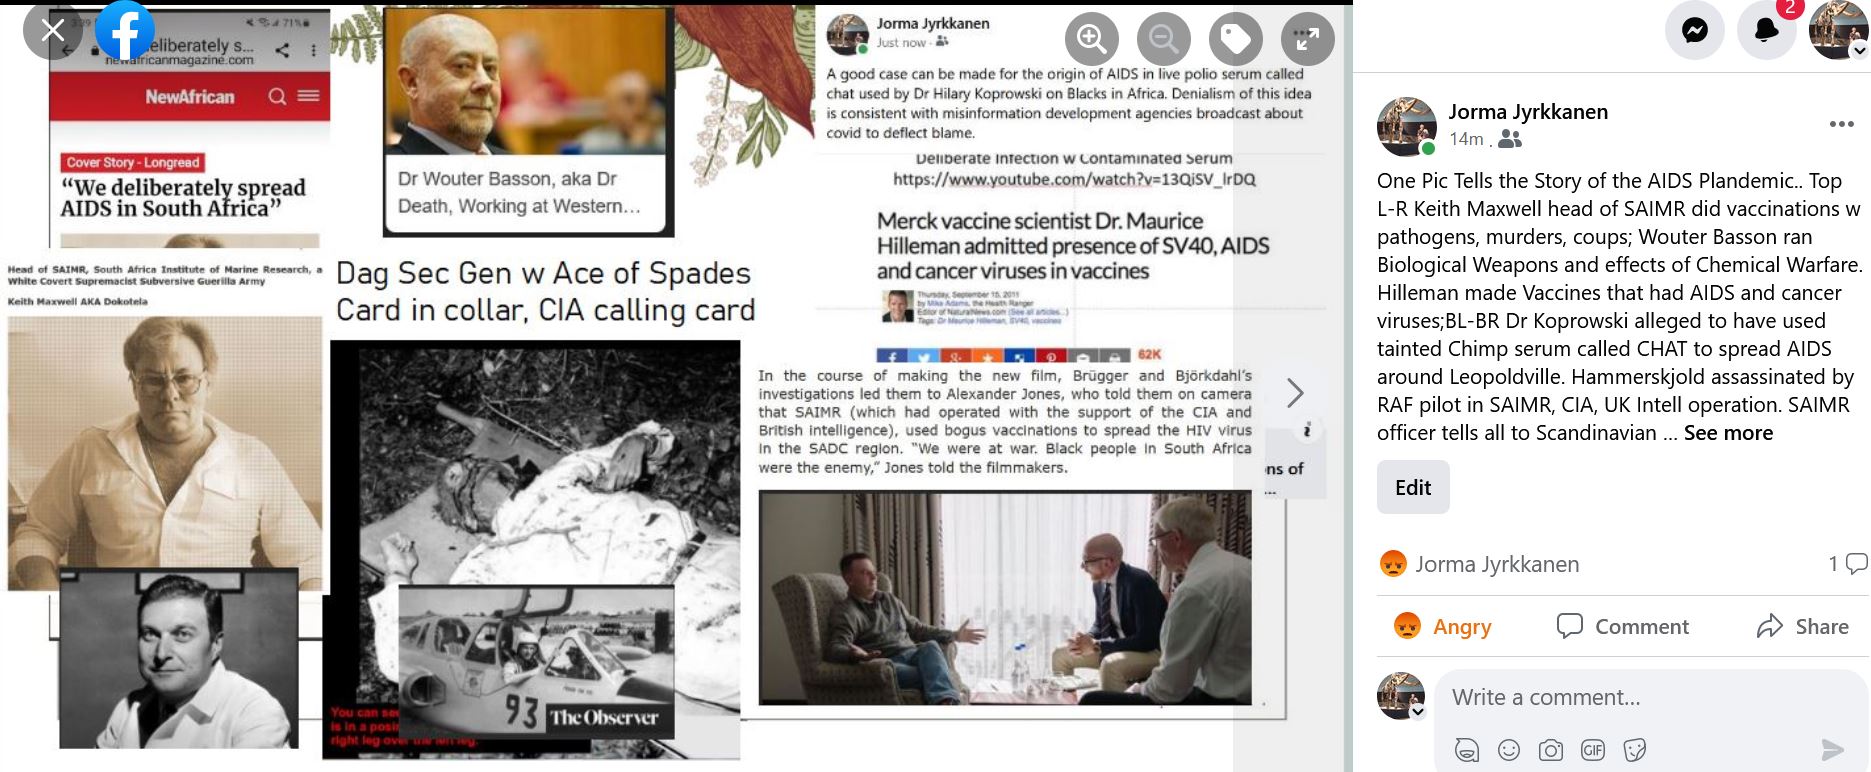
Some Favorite Pics I Shared. Jorma A Jyrkkanen, BSc, PDP, RWR Pfc-1st Class

June 5, 2023

Antibiotics, Vaccines, Polio, Viruses, Autoimmune Diseases, Bioterrorism-cont. Dr Tent Blows the Lid. 2023-06-03. Jorma A Jyrkkanen, BSc, PDP, Analyst

June 3, 2023
Antibiotics came out in 1942. In 1943 Polio broke out and kids were being paralyzed. What was in the vaccines that was causing polio? Monkey viruses were the prime suspect. His story is all about vaccines having all kinds of viruses that cause cancer and other diseases. In 1955 a polio vaccine was rushed into production. They put formaldehyde into the vaccine. Dr. Bernice Eddy said it should be tested first. They did on Monkeys and they became paralyzed. Kids got sick from polio vaccine and were paralyzed. The polio vaccine never stopped polio. Better sanitation stopped it.

Deadly Viruses Were Being Disseminated in Vaccines

Inner Connections>Welcome to Inner Connections>Cafe>Cafe, Fun Things Archived>

The Exploding Autoimmune Epidemic – Dr. Tent – It’s Not Autoimmune, you have Viruses.
Crochet Sue IC Angel

Jan 29, 2013#1
The Exploding Autoimmune Epidemic – Dr. Tent – It’s Not Autoimmune, you have Viruses.
This is about vaccines, they contain viruses that cause all kinds of diseases.
I am watching this video and it is very interesting. It’s 2 hrs long and I realize most do not have the time to watch it so I’m taking notes. I was taking notes for one of my sisters, and decided to post them here too. I have only watched
a half hour so far and will post the notes I took below. I will post more as I watch it, which I won’t be watching anymore tonight, but over the next few days.
In this first half hour he is talking about the vaccines causing cancer. He hasn’t talked about vaccines causing autoimmune diseases yet. I am interested to get to that part as scleroderma, which Gabby had, {I Jorma Jyrkkanen have scleroderma and have had Polio vaccines as a kid in about 1951} is also an
autoimmune disease that starts out the same as arthritis but gets much worse when it attacks internal organs.

Jan 29, 2013#2
Notes from the first half hour:
They thought a virus was the cause of cancer in the early 50’s
In 1999 to 2001, 60 Minutes investigated this story and they put more money
and time into than any other story they ever aired. They said there is no way
they can air this so they didn’t.
1942 antibiotics were released, 1943 polio became an epidemic. Polo mimicked
the flu so people were treated with antibiotics when they really had polo
.
1955 a polo vaccine was rushed into productions. They put formaldeyde in
the vaccine. Dr. Bernice Eddy said they should test it first, she tried it on
monkeys and they were paralyzed. She tried to get them to halt the vaccine
but they did it anyway. Kids got sick from polio and were paralyzed.

The polo vaccine never stopped polio, it was stopped by people practicing
better santitation and refrigeration methods.
Dr. Eddy was taken off the polio research. She and Dr. Sarah Stewart discovered
that cancer is caused by a virus.

The vaccine manufacturers were growing their polio viruses on the kidneys
of monkeys and when they removed the polio virus from the monkey kidneys
they also removed an unknown number of other monkey viruses with it.
In 1959 Dr. Bernice Eddy found overwhelming evidence that they had just
inoculated an entire generation with cancer-causing monkey viruses.
She predicted an epidemic of cancer. There is 40 monkey viruses in
the vaccines. [JJ comment: SV40 is the culprit we now know]
The government made it classified and would no longer allow information
about it out to the public. Everyone still has these viruses from the vaccines inside of them. If you get
a blood sample analyzed they would find these viruses in it.

In 1960 Dr. Bernice Eddy gave a talk to the New York Cancer Society and announced
that she examined the monkey kidney cells in which the polio virus was grown and
found they were infected with cancer-causing viruses, SV-40.
They crushed Bernice Eddy professionally. They took away her lab, destroyed
her animals, put her under a gag order and delayed publication of her scientific
papers.
In 1961 federal regulations went into effect that required that the polio vaccines
be free of SV40 but they did NOT require the SV40 contaminated seeds used to
make every batch or lot of vaccine be discarded nor the recently manufactured
contaminated vaccines be discarded. They continued giving the contaminated
vaccines to children and adults until they were used up sometime in 1963.
In 1962 Sabin Oral Polio vaccine is introduced but they used the same culture
medium, the monkey kidneys. This was the vaccine put into the sugar cube
that everyone took back then. It is estimated that 1 out of every 200 people
are getting cancer caused by SV40.

They started to realize that cancers rarely seen such as lung, breast, prostate,
lymphoma, brain and melanoma increased 50% over a 16 year period. Lung
cancer is rising because the vaccine is causing it, not smoking. As smoking has
gone down, lung cancer has gone up.

The vaccine developers did not want to release this information. They said it
would scare the public unnecessarily. If they hear that their children were
injected with a cancer virus that would not be very good.
Men born between 1948 and 1957 have 3x as much cancer not related to smoking.
The study’s researchers insist the increase cannot be explained by smoking,
better diagnosis or an again population. Public Health Official, Devra Lee Davis
said “There’s something else going on here.”
The SV40 virus is also sexually transmitted and you can get it from a blood
transfusion and it is spread from mother to child even if they had never got the
vaccine shots. Those never inoculated with the contaminated vaccine inherits it
up from their parents and can pass it on or infect their children and grandchildren.
This information has been blacked out from history.

There is also a virus in the vaccine that acts like AIDS.
Robert Gallo’s group at the NCI and Litton Bionetics also experimented with other
simian and human cancer viruses (e.g., SV40), and developed recombinants (i.e. mutants)
of these with other viral nucleic acids including those that caused the prominent
features of AIDS — WBC dysfunction, leukemias, lymphomas, sarcomas,
progressive wasting, and ultimate death in cats, mice, chickens, and humans.

See also https://www.facebook.com/TruthIsTerrorism/videos/maurice-hilleman-was-responsible-for-developing-more-than-40-vaccines-including-/1955638617986347/

SV40 and HIV fragment found in covid-19 vaccines. This suggest bioterrorists are still using experience from the 1950s and 1960s to make people sick by producing epidemics and big profits for Big Pharma.

Pentagon Global Biowarfare Program. Liz Churchill. 2023-05-29. Analyst Jorma Jyrkkanen, BSc, PDP

May 29, 2023

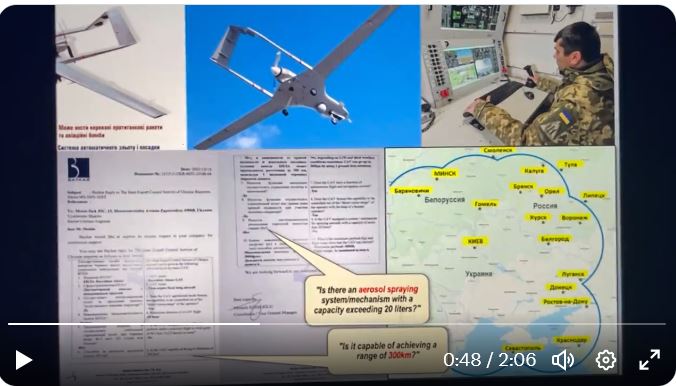
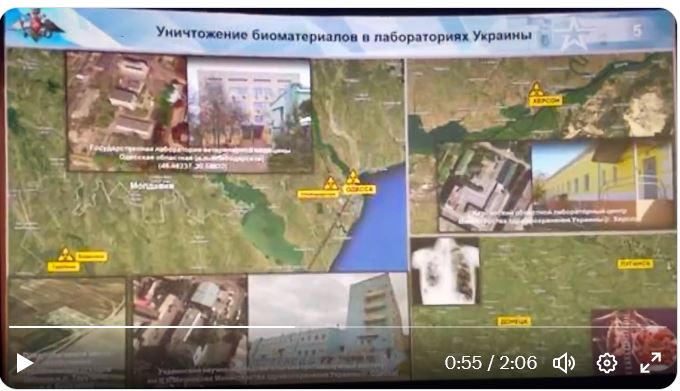
https://twitter.com/i/status/1662566656432910339

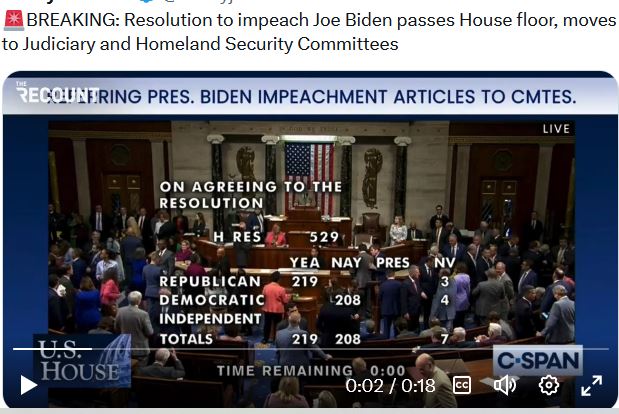
Vote to Impeach Biden Passes

← Back

Thank you for your response. ✨

Wuhan Institute of Virology Shao Cao Admission Wuhan Lab Participated in the Search for Best ACE2 Adherent Spike for Weaponization

PERPETRATORS OF THIS HEINOUS CRIME AGAINST HUMANITY

My Summary

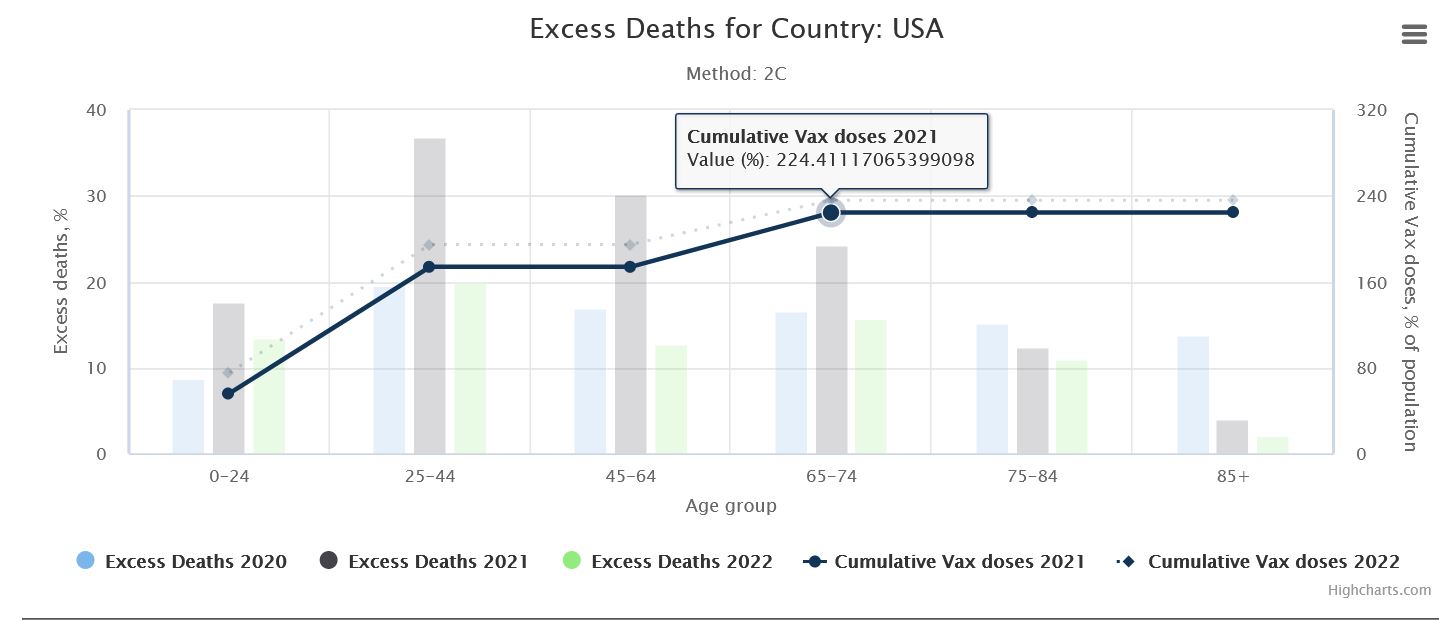
The covid-19 virus was designed to harm the immune system by attacking the mitochondrial contribution and the AIDS fragment was included to further attack the immune system. The SV40 fragment found by Japanese investigators is a cancer promoter and specifically can produce several cancers including the same one as asbestos. Loss of the mitochondria increases reactive oxygen and lipid peroxide the same as antibiotics and common pesticides. These are mutagens that can initiate many changes including but not limited to increasing the risk of cancer while loss of oxidative phosphorylation will increase aerobic glycolysis, the favorite respiration of cancer while also damaging the cardiovascular system because the heart is loaded with and mitochondria and needs them as an ATP energy source. You also lose short chain fatty acids which damages the immune system. Mitochondrial genes sustain the immune system and that contribution is diminished by their damage or loss. Data from a number of countries showed that deaths increased significantly after vaccinations. The mRNA experimental drugs are not a vaccine. They neither prevent infection or stop its spread. They don’t work because this virus mutates faster than we can make vaccines. This virus is a population reduction biowarfare agent designed to kill people and the vaccine is part of that mission. Administration of antibiotics to those sick with it may hasten their death. Please see: https://www.researchgate.net/publication/346505752_Antibiotic_induced_changes_to_mitochondria_result_in_potential_contributions_to_carcinogenesis_heart_pathologies_other_medical_conditions_and_ecosystem_risks

See my findings on mitochondria important in considering future side effects.

The Chief Architects of this Depravity

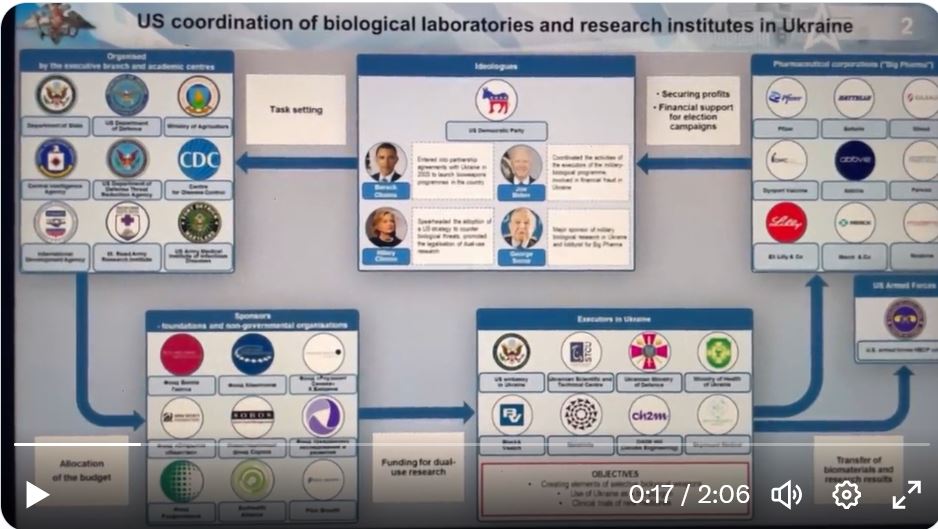
Obama, Biden, Hillary, Many others.

CBC Story on Manitoba Lvl IV Lab Suggest Canada Researching Bioweapons. Is this under contract to US DOD?

These Biological Weapons Revelations Changes Everything

These Revelations Change the Direction and Purpose of the Phony Proxy War from Protection of Sovereignty to Protection of Global Biological War Infrastructure and Perpetrators to Arresting them for Crimes against Humanity and Contributing to Ecocide for Trial at Nuremberg II.

SEE ALSO https://jormajyrkkanen.ca/2023/01/13/jorma-antero-jyrkkanens-bibliography-2022/

← Back

Thank you for your response. ✨

BigPharma Biggest Harma

https://twitter.com/i/status/1708585468479123516

Kennedy Writes Book on this Subject

Hydroxychloroquine (HCQ) Flips from Not Good (June 2021) to Good it Works with Azithromycin(April 2023). 2023-04-09. Jorma Jyrkkanen, BSc, PDP

April 10, 2023

Sunday, April 9, 2023

Hydroxychloroquine (HCQ) Flips from Not Good (June 2021) to Good it Works with Azithromycin (April 2023). 2023-04-09.

During early Pandemic nature scientific reports articles Hydroxychloroquine plus standard of care compared with standard of care alone in COVID-19: a meta-analysis of randomized controlled trials Open Access Published: 07 June 2021 Hydroxychloroquine plus standard of care compared with standard of care alone in COVID-19: a meta-analysis of randomized controlled trials Bahman Amani, Ahmad Khanijahani & Behnam Amani Scientific Reports volume 11, Article number: 11974 (2021) Cite this article 4674 Accesses 12 Citations 41 Altmetric Metrics details Abstract The efficacy and safety of Hydroxychloroquine (HCQ) in treating coronavirus disease (COVID-19) is disputed. This systematic review and meta-analysis aimed to examine the efficacy and safety of HCQ in addition to standard of care (SOC) in COVID-19. PubMed, the Cochrane Library, Embase, Web of sciences, and medRxiv were searched up to March 15, 2021. Clinical studies registry databases were also searched for identifying potential clinical trials. The references list of the key studies was reviewed to identify additional relevant resources. The quality of the included studies was evaluated using the Cochrane Collaboration tool and Jadad checklist. Meta-analysis was performed using RevMan software (version 5.3). Eleven randomized controlled trials with a total number of 8161 patients were identified as eligible for meta-analysis. No significant differences were observed between the two treatment groups in terms of negative rate of polymerase chain reaction (PCR) (Risk ratio [RR]: 0.99, 95% confidence interval (CI) 0.90, 1.08; P = 0.76), PCR negative conversion time (Mean difference [MD]: − 1.06, 95% CI − 3.10, 0.97; P = 0.30), all-cause mortality (RR: 1.09, 95% CI 1.00, 1.20; P = 0.06), body temperature recovery time (MD: − 0.64, 95% CI − 1.37, 0.10; P = 0.09), length of hospital stay (MD: − 0.17, 95% CI − 0.80, 0.46; P = 0.59), use of mechanical ventilation (RR: 1.12, 95% CI 0.95, 1.32; P = 0.19), and disease progression (RR = 0.82, 95% CI 0.37, 1.85; P = 0.64). However, there was a significant difference between two groups regarding adverse events (RR: 1.81, 95% CI 1.36, 2.42; P < 0.05). The findings suggest that the addition of HCQ to SOC has no benefit in the treatment of hospitalized patients with COVID-19. Additionally, it is associated with more adverse events. Today 2023-04-09

Summary Conclusion

Hydroxychloroquine (HCQ) Good or Bad (June 2021). The Jury May Have Just Changed its Mind (April 2023).

at April 09, 2023

Email ThisBlogThis!Share to TwitterShare to FacebookShare to Pinterest

Labels: covid, hydroxychloroquine, saves lives, study, works

Special Report: Former Labradoodle breeder was tapped to lead U.S. pandemic task force. Jorma Jyrkkanen bSC, PDP, Investigation into and Repost. 2023-04-06

April 7, 2023

Healthcare & Pharma

April 22, 20202:23 PMUpdated 3 years ago

By Aram Roston, Marisa Taylor

13 Min Read OPERATION WARP SPEED

WASHINGTON (Reuters) – On January 21, the day the first U.S. case of coronavirus was reported, the secretary of the Department of Health and Human Services appeared on Fox News to report the latest on the disease as it ravaged China. Alex Azar, a 52-year-old lawyer and former drug industry executive, assured Americans the U.S. government was prepared.Centers for Disease Control (CDC) Director Dr. Robert Redfield, U.S. Department of Health and Human Services Chief of Staff Brian Harrison and HHS Secretary Alex Azar meet about the novel coronavirus outbreak in this HHS handout photo taken in Washington, U.S. January 22, 2020. Picture taken January 22. 2020. U.S. Department of Health and Human Services/Handout via REUTERS

“We developed a diagnostic test at the CDC, so we can confirm if somebody has this,” Azar said. “We will be spreading that diagnostic around the country so that we are able to do rapid testing on site.”

While coronavirus in Wuhan, China, was “potentially serious,” Azar assured viewers in America, it “was one for which we have a playbook.”

Azar’s initial comments misfired on two fronts. Like many U.S. officials, from President Donald Trump on down, he underestimated the pandemic’s severity. He also overestimated his agency’s preparedness.

As is now widely known, two agencies Azar oversaw as HHS secretary, the Centers for Disease Control and Prevention and the Food and Drug Administration, wouldn’t come up with viable tests for five and half weeks, even as other countries and the World Health Organization had already prepared their own.

Shortly after his televised comments, Azar tapped a trusted aide with minimal public health experience to lead the agency’s day-to-day response to COVID-19. The aide, Brian Harrison, had joined the department after running a dog-breeding business for six years. Five sources say some officials in the White House derisively called him “the dog breeder.”

Azar’s optimistic public pronouncement and choice of an inexperienced manager are emblematic of his agency’s oft-troubled response to the crisis. His HHS is a behemoth department, overseeing almost every federal public health agency in the country, with a $1.3 trillion budget that exceeds the gross national product of most countries.

Azar and his top deputies oversaw health agencies that were slow to alert the public to the magnitude of the crisis, to produce a test to tell patients if they were sick, and to provide protective masks to hospitals even as physicians pleaded for them.

The first test created by the CDC, meant to be used by other labs, was plagued by a glitch that rendered it useless and wasn’t fixed for weeks. It wasn’t until March that tests by other labs went into production. The lack of tests “limited hospitals’ ability to monitor the health of patients and staff,” the HHS Inspector General said in a report this month. The equipment shortage “put staff and patients at risk.”

A promised virus surveillance program failed to take root, despite assurances Azar gave to Congress. Rather than share information, three current and three former government officials told Reuters, Azar and top staff sidelined key agencies that could have played a higher-profile role in addressing the pandemic. “It was a mess,” said a White House official who worked with HHS.

Officials across the government, from President Trump on down, have been blasted for America’s halting response to the pandemic. Critics inside and outside the administration say a meaningful share of the responsibility lies with HHS and Trump appointee Azar.

“You have to blame the problem on the virus, but it’s Azar’s operation,” said Lynn Goldman, the dean of the public health school at George Washington University, who has served on advisory boards of the FDA and CDC. “And the buck stops there.”

HHS declined to make Azar available for an interview. Michael Caputo, the new chief HHS spokesman, declined to answer Reuters questions about Azar’s stewardship, saying in a statement: “We are communicating to the American public during a deadly pandemic.”

DALLAS LABRADOODLES

Azar is a Republican lawyer who once clerked for the late conservative Supreme Court Justice Antonin Scalia and counts current Supreme Court Justice Brett Kavanaugh as a friend. Under George W. Bush, Azar worked for HHS as general counsel and deputy secretary. During the Obama years, he cycled through the private sector as a pharmaceutical company lobbyist and executive for Eli Lilly. After Trump’s first HHS secretary was forced out in a travel corruption scandal, Azar stepped in, in January 2018.
Two years later, at the dawn of the coronavirus crisis, Azar appointed his most trusted aide and chief of staff, Harrison, as HHS’s main coordinator for the government’s response to the virus.

Harrison, 37, was an unusual choice, with no formal education in public health, management, or medicine and with only limited experience in the fields. In 2006, he joined HHS in a one-year stint as a “Confidential Assistant” to Azar, who was then deputy secretary. He also had posts working for Vice President Dick Cheney, the Department of Defense and a Washington public relations company.

Before joining the Trump Administration in January 2018, Harrison’s official HHS biography says, he “ran a small business in Texas.” The biography does not disclose the name or nature of that business, but his personal financial disclosure forms show that from 2012 until 2018 he ran a company called Dallas Labradoodles.

The company sells Australian Labradoodles, a breed that is a cross between a Labrador Retriever and a Poodle. He sold it in April 2018, his financial disclosure form said. HHS emailed Reuters that the sale price was $225,000.

At HHS, Harrison was initially deputy chief of staff before being promoted, in the summer of 2019, to replace Azar’s first chief of staff, Peter Urbanowicz, an experienced hospital executive with decades of experience in public health.

This January, Harrison became a key manager of the HHS virus response. “Everyone had to report up through him,” said one HHS official.Slideshow ( 2 images )

One questionable decision, three sources say, came that month, after the White House announced it was convening a coronavirus task force. The HHS role was to muster resources from key public health agencies: the CDC, FDA, National Institutes of Health, Office of Global Affairs and the Assistant Secretary for Preparedness and Response.

Harrison decided, the sources say, to exclude FDA Commissioner Stephen Hahn from the task force. “He said he didn’t need to be included,” said one official with knowledge of the matter.

When task force members were announced January 29, neither Hahn nor the FDA were included. Hahn wasn’t put on the task force until Vice President Mike Pence took over in February. Two of Hahn’s high-profile counterparts were on it from the start: CDC director Robert Redfield and Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases.

The HHS denied it was Harrison’s decision to leave out Hahn and the FDA, but declined to say who made the call. The agency lauded Harrison’s work on the task force.

In a statement, Hahn said the FDA was focused on the coronavirus epidemic, “not on when we were added to the task force,” and that the agency was not “excluded.”

Fauci, who has become a public face of the Trump Administration’s COVID-19 effort, said he wasn’t sure including the FDA was necessary at the start. Initially, the Chinese government was saying the virus spread through animals, not human to human, he said. “You would include the FDA when you want to expedite drugs or devices,” Fauci said.

Others said the lack of a strong FDA role early on had direct consequences. Two sources familiar with events say the White House wasn’t getting information from the FDA about the state of the testing effort, a crucial element of the coronavirus response.

Reached by phone, Harrison declined to answer Reuters’ questions. In a later statement, he did not address questions about the task force but said he was proud of his work history. “Americans would be well served by having more government officials who have started and worked in small family businesses and fewer trying to use that experience to attack them and distort the record,” he wrote.

In a statement to Reuters, Azar said Harrison has been an asset. “From day one, Brian has demonstrated remarkable leadership and managerial talents,” Azar wrote.

LOW RISK?

In the pandemic’s early days, Azar offered words of both concern and assurance in public. On January 31, a day after the WHO declared COVID-19 a global health emergency, Azar declared it a public health emergency.

That same day, during the first Coronavirus Task Force briefing, Azar told the public: “I want to stress: The risk of infection for Americans remains low.”

The United States, he said, had taken adequate precautions. Travel restrictions and 14-day quarantines on Americans who had been to Wuhan, where the virus originated, were imposed. Americans returning from other parts of China had to self-quarantine.

The next week, on February 7, in another press conference, Azar repeated the message. “The immediate risk to the American public is low at this time,” he announced.

Behind the scenes, his aides say, Azar had alerted the White House in early January, and then later that month spoke directly to the president. It is unclear exactly what Azar told the president, because transcripts are not available.

“There’s a lot of CYA going on,” said one senior administration official, who said Azar never spelled out that stockpiles of protective equipment might be inadequate or the tests were not working. “We were told the test was ready. That turned out to be flat-out wrong.”

Trump denied Azar sent out alarms. “@SecAzar told me nothing until later,” he tweeted earlier this month.

Meanwhile, Azar continued to say “the immediate risk” to Americans was low and that travel restrictions had worked. “So I think so far, our measures have been quite effective,” he told NPR on February 14.

Others were raising alarms. “It’s not so much of a question of if this will happen any more, but rather more of a question of exactly when this will happen,” Dr. Nancy Messonnier, director of the National Center for Immunization and Respiratory Diseases, said at a February 25 news briefing.

MORE GLITCHES

Responding to Congressional concerns, Azar said HHS had launched a coronavirus surveillance system in five cities. The plan was to test patients who showed up with flu symptoms, to see if they actually were infected with the novel coronavirus.

But the system was either delayed or not implemented in the cities and now is seen by epidemiologists as irrelevant given the massive community spread and continued inadequate testing.

By the end of February, Azar sought more money to attack the crisis as he testified before Congress. “This is an unprecedented potentially severe health challenge globally, and will require additional measures,” he said.

Still, he assured senators his agency was in control. “We have enacted the most aggressive containment measures in the history of our country,” he said.

He again provided words of calm, appearing on Fox News. “But thanks to President Trump’s historically aggressive containment efforts, we’ve actually contained the spread of this virus here in the United States at this point,” he said February 25. “I think part of the message to the American people is we all need to take a bit of deep breath here.”

“The government is working on this. You’ve got the right people on this.”

By the end of February, Azar and Harrison were no longer running the White House task force. That month, Vice President Pence took control. The FDA and Hahn are now actively involved. A Pence spokesperson said the issue of precluding the FDA from the task force “pre-dates the VP’s leadership” and declined further comment.

Azar seemed caught off guard by the change. “I’m still chairman of the task force,” he told the press after Pence took over.

Given Azar’s early struggles, the White House should have taken a stronger role over the task force from the outset, said Ashish Jha, director of Harvard University’s Global Health Institute. “It was very clear that Azar wasn’t able to marshal the forces across the government like he needed to,” he said.

Jeffrey Flier, a former Harvard Medical School dean, said the HHS role remains as vital as ever. As of Wednesday, over 47,000 Americans have died of COVID-19, and more than 830,000 have been infected.

“Clearly there was a need for better coordination of the FDA and CDC and other agencies,” he said. “HHS has to be operating effectively in a crisis like this.”

Reporting by Aram Roston and Marisa Taylor in Washington. Editing by Ronnie Greene

Our Standards: The Thomson Reuters Trust Principles.

PLANDEMIC SUMMARY BY SPARTA JUSTICE; SOME PERPS AND THEIR PARTICIPATION, Analyst Jorma Jyrkkanen 2024-03-25

March 25, 2023

CRIMES OF WEF AND DEEP STATE BIDEN OBAMA HILLARY AND COMPANY

https://twitter.com/SpartaJustice/status/1700798065290936680

Proof of Plandemic

HOW THEY DID IT: They used a particular bug (Coronavirus) that was previously relatively benign and nonpathogenic and modified it through the use of gene editing techniques to make the bug (Covid-19) virulent, pathogenic, dangerous and then released that bug (Covid) in key sites.… Show mor

THEY RELEASED COVID-19: U.S. Patents show CDC ownership of Coronavirus. Both China and the U.S. involved in creating SARS-CoV-2. Bill Gates and CCP appoints criminal Tedros of WHO. The DOD, FDA, CIA, NIH, Fauci, Baric, Daszak, Rockefeller, Rothschilds are all involved in these Crimes.

Bill Gates and the Rockefeller foundation paid Google, Facebook, Politico, Wikipedia, Fact Checkers in order to censor and control all the information. The CIA has been using Operation Mockingbird for years and has over 3,000 agents implanted in Mainstream Media to control the population. Event 201 was sponsored by Bill Gates, the Johns Hopkins Center for Health Security (CIA) and the World Economic Forum to enforce a worldwide Pandemic response 5 months before the WHO fraudulently declared a global pandemic.

It was a planned coordinated criminal effort worldwide. In January 2017 Anthony Fauci said there will be a surprise virus outbreak before the end of 2020. Bill Gates in 2015 talked of a future pandemic and lied in April 2020 when he said they did not simulate or practice for a pandemic.

Klaus Schwab in his book Covid-19 The Great Reset shows Covid was the Trojan Horse to Reset the World according to the UN 2030 Agenda. Build Back Better slogan is a criminal coordinated effort to remove human rights and institute a one world government.

Bill Gates and the Rockefeller foundation bribes the WHO, NIH, NIAID, CDC, FDA, Medical Schools and Journals to control the health industry and public health policy.

WHO Chief Tedros involved in genocide killing and torture in Ethiopia. Tedros is a known member of the communist party. He is Beijing’s and Gates puppet. As a Health Minister he was accused of covering up three Cholera Epidemics and committing crimes against humanity. CCP and Bill Gates helped put Tedros in charge of the WHO. John D. Rockefeller over 100 years ago seized the U.S. Media and took control over public health using toxic petroleum based drugs for profit and controlled the American Medical Association blacklisting and expelling any doctors who practiced natural medicine. Rockefeller’s poison injections and medicines started causing cancer in early years and to cover it up formed the American Cancer Society. Medical error is the 3rd leading cause of death in America.

Bill Gates used India and Africa as guinea pigs for pharmaceutical companies to make a financial killing while killing a lot of people in the process including killing innocent children and babies with vaccines. Bill Gates controls GAVI The Vaccine Alliance to vaccinate the world with his poisons.

National Security Study Memorandum NSSM 200 Implications of Worldwide Population Growth For U.S. Security and Overseas Interests December 10, 1974 (THE KISSINGER REPORT) shows the intention of governments to reduce the population. Bill Gates is one of the key funders in the Stratosphere experiment to block out the sun for Climate Change by releasing poisons in the air. Environmental Scientist call it global genocide experiment.

Gates has invested over one billion dollars in the Earth Now Global Surveillance project to launch hundreds of satellites to monitor people everywhere 24/7 a day. In partnership with MIT Bill Gates has developed a new technology that allows vaccines to be injected under your skin along with your medical records. Bill Gates Gates funded genetically modified mosquitoes released in the USA to allow human immunization by means of mosquito bites “Flying Syringes.” Gates had business dealings and a relationship with Jeffrey Epstein, a convicted child sex criminal. Why would he choose to partner with the world’s most notorious pedophile? Gates is the top financial donor of the WHO and CDC. No one person has more power than Gates to influence and control the health and medical freedom of all people. Bill Gates and all mRNA Vaccines must be stopped. This is a global genocide experiment and a takeover of humanity.

https://twitter.com/i/status/1638756789951909889

Acute autoimmune-like hepatitis with atypical anti-mitochondrial antibody after mRNA COVID-19 vaccination: A novel clinical entity or general response? Addendum is it the body’s reaction to Spike Protein-Jorma Jyrkkanen 2023-03-23

March 23, 2023

Reference: Ghielmetti M, Schaufelberger HD, Mieli-Vergani G, Cerny A, Dayer E, Vergani D, Terziroli Beretta-Piccoli B. Acute autoimmune-like hepatitis with atypical anti-mitochondrial antibody after mRNA COVID-19 vaccination: A novel clinical entity? J Autoimmun. 2021 Sep;123:102706. doi: 10.1016/j.jaut.2021.102706. Epub 2021 Jul 15. PMID: 34293683; PMCID: PMC8279947.

Abstract

Autoimmune phenomena and clinically apparent autoimmune diseases, including autoimmune hepatitis, are increasingly been reported not only after natural infection with the SARS-CoV-2 virus, but also after vaccination against it. We report the case of a 63-year old man without a history of autoimmunity or SARS-CoV-2 natural infection who experienced acute severe autoimmune-like hepatitis seven days after the first dose of the mRNA-1273 SARS-CoV-2 vaccine. Liver histology showed inflammatory portal infiltrate with interface hepatitis, lobular and centrilobular inflammation with centrilobular necrosis, in absence of fibrosis and steatosis. Serum immunoglobulin G was slightly elevated. Autoimmune liver serology showed an indirect immuno fluorescence pattern on triple rodent tissue compatible with anti-mitochondrial antibody (AMA), but, unexpectedly, this pattern was not mirrored by positivity for primary biliary cholangitis (PBC)-specific molecular tests, indicating that this antibody is different from classical AMA. Anti-nuclear antibody (ANA) was also positive with a rim-like indirect immuno fluorescence pattern on liver and HEp2 cell substrates, similar to PBC-specific ANA; however, anti-gp210 and a large panel of molecular-based assays for nuclear antigens were negative, suggesting a unique ANA in our patient. He carries the HLA DRB1*11:01 allele, which is protective against PBC. Response to prednisone treatment was satisfactory. The clinical significance of these novel specificities needs to be further evaluated in this emerging condition.

Keywords: SARS-Cov-2, mRNA vaccine, Autoimmune-like hepatitis, Atypical anti-mitochondrial antibody

Jyrkkanen Comment: The mRNA-1273 SARS-CoV-2 vaccine vaccination appears to have induced anti-mitochondrial antibody AMA and anti-nuclear antibody ANA, suggesting the primary support genetic reservoirs of the host had turned antigenic and become autoimmune targets for attack by the hosts immune system. I suspect it is from spike protein. This autoimmune reaction would lead to the destruction of the source of ATP+NAD production and immune system integrity and would lead to and increased risk of cancer, heart disease and other medical conditions.

CONSEQUENCES OF LOSS OF A VACCINATED POPULATIONS’ IMMUNE INTEGRITY MIGHT BE BE AN INCREASE IN RARE DISEASES EX: MONKEY POX IN ISRAEL

Twitter Censors Pfizer-Injured Israeli COVID Vaccine Director

Prof. Shmuel Shapira MD MPH (Col.), who served as Director of the Israel Institute for Biological Research between 2013 and 2021, suggested that the monkeypox outbreak was connected to mRNA vaccines.

Aug 3, 2022

צילום: איליה מלניקוב

Professor Shmuel Shapira, M.D., MPH, served as the Director General of the Israel Institute for Biological Research (IIBR) between 2013 and 2021, where he led Israel’s effort to develop a coronavirus vaccine.

Prof. Shapira is also the founder and head of the Department of Military Medicine of the Hebrew University Faculty of Medicine and IDF Medical Corps. He is a Senior Research Fellow at the International Institute for Counter-Terrorism (ICT) at Reichman University in Israel.

Shapira previously served as Deputy Director General of the Hadassah Medical Organization and as the Director of the Hebrew University Hadassah School of Public Health. He is a Full Colonel (Res.) in the Israel Defense Forces (IDF) and served as the IDF Head of Trauma Branch.

He has published more than 110 peer-reviewed scientific articles and is the editor of Essentials of Terror Medicine, Best Practice for Medical Management of Terror Incidents, and Medical Response to Terror Threats.

Last week, Twitter censored Prof. Shapira—who was “physically injured” after his third Pfizer vaccine—and forced him to remove a post which said: “Monkey pox cases were rare for years. During the last years a single case was documented in Israel. It is well established the mRNA vaccines affect the natural immune system. A monkey pox outbreak following massive covid vaccination: *Is not a coincidence.”

Dr. Eli David @DrEliDavid

Prof. @shmuelcshapira, head of Israel Biological Institute (the most senior medical-scientific position in Israel) posted on the connection between monkeypox and you-know-what. Twitter locked his account and forced him to delete it. They know more about biology than him 🤡

Image

2:15 PM ∙ Jul 28, 2022

Antibiotics Use in Hospitalised COVID-19 Patients in a Tertiary Care Centre: Addendum and Heart Mitochondria by JORMA JYRKKANEN 2023-03-23

March 23, 2023

Antibiotics Use in Hospitalised COVID-19 Patients in a Tertiary Care Centre: A Descriptive Cross-sectional Study and Heart Mitochondria. JORMA JYRKKANEN 2023-03-23

Thapa B, Pathak SB, Jha N, Sijapati MJ, Shankar PR. Antibiotics Use in Hospitalised COVID-19 Patients in a Tertiary Care Centre: A Descriptive Cross-sectional Study. JNMA J Nepal Med Assoc. 2022 Jul 1;60(251):625-630. doi: 10.31729/jnma.7394. PMID: 36705203; PMCID: PMC9297358.

ABSTRACT
Introduction:

Antimicrobial resistance is a global health problem. The widespread and improper antibiotics use is the leading cause of antimicrobial resistance. Bacterial co-infection in COVID-19 patients is the basis for the use of antibiotics in the management of COVID-19. COVID-19 pandemic has seriously impacted antibiotic stewardship and increased the global usage of antibiotics, worsening the antimicrobial resistance problem. The use of antibiotics among COVID-19 patients is high but there are limited studies in the context of Nepal. This study aimed to find out the prevalence of antibiotic use among hospitalised COVID-19 patients in a tertiary care centre.

Introduction:

Antimicrobial resistance is a global health problem. The widespread and improper antibiotics use is the leading cause of antimicrobial resistance. Bacterial co-infection in COVID-19 patients is the basis for the use of antibiotics in the management of COVID-19. COVID-19 pandemic has seriously impacted antibiotic stewardship and increased the global usage of antibiotics, worsening the antimicrobial resistance problem. The use of antibiotics among COVID-19 patients is high but there are limited studies in the context of Nepal. This study aimed to find out the prevalence of antibiotic use among hospitalised COVID-19 patients in a tertiary care centre.
Methods:

A descriptive cross-sectional study was conducted on hospitalised COVID-19 patients from April 2021 to June 2021 in a tertiary care centre. Ethical approval was taken from the Institutional Review Committee (Reference number: 2078/79/05). The hospital data were collected in the proforma by reviewing the patient’s medical records during the study period of 2 months. Convenience sampling was used. Point estimate and 95% Confidence Interval were calculated.
Results:

Among 106 hospitalised COVID-19 patients, the prevalence of antibiotics use was 104 (98.11%) (95.52-100, 95% Confidence Interval). About 74 (71.15%) of patients received multiple antibiotics. The most common classes of antibiotics used were cephalosporins, seen in 85 (81.73%) and macrolides, seen in 57 (54.81%) patients.
Conclusions:

The prevalence of antibiotics use among hospitalised COVID-19 patients was found to be higher when compared to other studies conducted in similar settings.
Keywords: antibiotics, bacterial infection, co-infection, COVID-19
Go to:
INTRODUCTION

Antimicrobial resistance (AMR) is a major threat to global public health due to the increasing incidence of resistant human pathogens.1,2 The widespread and improper use of antibiotics is the leading cause of AMR.1 Coronavirus Disease 2019 (COVID-19) is a viral disease thus untreatable by antibiotics, but the viral respiratory infections may clinically progress to bacterial pneumonia requiring antibiotic administration.2 This co-pathogenesis is the basis for use of antibiotics in COVID-19. But appropriate use of antibiotics is utmost to prevent AMR.

COVID-19 pandemic has seriously impacted antibiotic stewardship and single-handedly increased the global usage of antibiotics, causing a cascading effect on the AMR problem. The use of antibiotics among COVID-19 patients is high but there are limited studies in the context of Nepal.3-5

This study aimed to find out the prevalence of antibiotics use among COVID-19 patients of a tertiary care centre.
Go to:
METHODS

A descriptive cross-sectional study was conducted at KIST Medical College and Teaching Hospital after taking ethical approval from the Institutional Review Committee (Reference number: 2078/79/05). The study was conducted during the study period from 6 August 2021 to 6 October 2021 during which hospitalised COVID-19 patients admitted from April 2021 to June 2021 were studied. All the COVID-19 cases confirmed by reverse transcriptase polymerase chain reaction (RT-PCR) test who were admitted in the dedicated COVID-19 ward, high dependency unit (HDU) and intensive care units (ICU) were enrolled. Patients who had incomplete documentation were excluded from the study. Convenience sampling was used. The sample size was calculated using the following formula:
n=Z2×p×qe2=1.962×0.50×0.500.102=97

Where,

n = minimum required sample size
Z = 1.96 at 95% Confidence Interval (CI)
p = prevalence taken as 50% for maximum sample size calculation
q = 1-p
e = margin of error, 10%

Minimum sample size calculated was 97. However, we enrolled 106 cases. The collected data from hospital records was entered in the proforma by reviewing the patient’s medical records during the study period of two months. Demographic profile of patients like age and sex, clinical profile like co-morbidity and disease severity, management profile like level of care required for patients’ treatment, number and type of antibiotics used, route of antibiotic administration, duration of antibiotics used, and estimated cost of antibiotics used for the treatment were assessed. The patients who were treated with at least one antibiotic were included. All the cases were classified as a mild disease, moderate disease, or severe disease.6

In our study, 17 different antibiotics were used belonging to seven different antibiotic classes. They are namely cephalosporin (ceftriaxone, cefixime, cefoperazone, and cefepime), macrolides (azithromycin, clindamycin, and erythromycin), penicillin group (piperacillin, amoxicillin), quinolones (moxifloxacin, levofloxacin, ciprofloxacin), imidazoles (metronidazole), carbapenem (meropenem) and beta-lactamase inhibitors (clavulanic acid, tazobactam, sulbactam).

The data were entered and analysed using IBM SPSS Statistics 21.0. Point estimate and 95% CI were calculated.
Go to:
RESULTS

Among 106 hospitalised COVID-19 patients, the prevalence of use of antibiotics was 104 (98.11%) (95.52-100, 95% CI). The mean number of antibiotics used per patient was 1.86 ±0.64. A total of 74 (71.15%) patients were under two or more antibiotic therapy. Around 60 (57.69%) patients were treated with intravenous as well as per oral route of administration of antibiotics.

The mean number of days of admission was 6.44±4.81 days. The mean duration of antibiotics use was 6.33 ±2.72 days. About 30 (28.85%) received a 5 day course of antibiotics while 25 (24.04%) patients received a 7 days course of antibiotics. Only 23 (22.12%) received antibiotic therapy for more than 7 days. The mean estimated expenditure on antibiotics was NPR 4,645±8, 498 (USD 38.71±70.82) (Table 1).
Table 1
Use of antibiotics in management of COVID-19 patients (n = 104).
Characteristics n (%)
Number of antibiotics used
1 30 (28.85)
2 59 (56.73)
3 15 (14.42)
Route of antibiotics
Intravenous route only 37 (35.58)
Per oral route only 7 (6.73)
Intravenous and per oral route 60 (57.69)
Total number of days of antibiotics use
≤7 days 81 (77.88)

7 days 23 (22.12)
Estimated expenditure on antibiotics therapy NPR (US dollar)
≤1,200 (USD 10) 43 (41.35)
1201 to 6,000 (USD 11 to 50) 42 (40.38)
6,001 to 12, 000 (USD 51 to 100) 8 (7.69)
12,001 to 24,000 (USD 101 to 200) 7 (6.73)
24,000 (USD 200) 4 (3.85)
Open in a separate window

The mean age of the patients was 55.84±18 years. A total of 54 (51.92%) patients were males. Around 59 (56.73%) had at least one comorbid condition with the most common conditions being hypertension seen in 39 (37.50%) and diabetes mellitus seen in 23 (22.16%) (Table 2).
Table 2
Demographic characteristics of hospitalised COVID-19 patients who received antibiotic therapy (n= 104).
Age group n (%)
≤20 years 5 (4.81)
21 to 40 years 18 (17.31)
41 to 60 years 37 (35.58)
61 to 80 years 37 (35.58)

80 years 7 (6.73)
Sex
Males 54 (51.92)
Females 50 (48.08)
Comorbidities
Diabetes mellitus 23 (22.16)
Hypertension 39 (37.50)
Chronic Obstructive Pulmonary 10 (9.62)
Disease (COPD)
Hypothyroidism 12 (11.54)
Psychiatric illness 2 (1.92)
Heart failure 2 (1.92)
Autoimmune disease 2 (1.92)
Chronic kidney disease 1 (0.96)
Open in a separate window

Severe COVID-19 represented 37 (35.58%) of total patients, 16 (15.38%) of them were managed in ICU with ventilator support. Moderate COVID-19 cases also accounted for 37 (35.58%) of total patients. These patients were mostly managed in a dedicated COVID-19 ward with 2 (1.92%) cases managed in ICU and 2 (1.92%) in HDU. All 30 (28.84%) mild cases were managed in the ward (Table 3).
Table 3
COVID-19 severity and level of care received by the patients who received antibiotic therapy (n = 104).
Level of care Mild n (%) Moderate n (%) Severe n (%) Total n (%)
ICU with ventilator support – – 16 (15.38) 16 (15.38)
ICU without ventilator support – 2 (1.92) 4 (3.85) 6 (5.77)
HDU – 2 (1.92) 15 (14.42) 17 (16.35)
Ward 30 (28.84) 33 (31.73) 2 (1.92) 65 (62.50)
Open in a separate window

The most common class of antibiotics used was cephalosporins in 85 (81.73%) patients followed by macrolides in 57 (54.81 %). Cefixime used in all cases was a substitute for ceftriaxone in oral form in 18 (17.31%) patients who were previously prescribed ceftriaxone. Beta-lactamase inhibitors were used in 35 (33.65%) in conjunction with penicillin (amoxicillin) or cephalosporin group of drugs (cefoperazone, cefepime). The most common combination used was cephalosporin with macrolides at 38 (36.54%) (Table 4).
Table 4
Types of antibiotics used in management of COVID-19 patients (n = 104).
Antibiotics n (%)
Cephalosporins prescribed parenterally 85 (81.73)
Ceftriaxone 76 (73.08)
Cefepime sulbactam 3 (2.88)
Cefoperazone sulbactam 6 (5.77)
Cephalosporins prescribed enterally 18 (17.31)
Cefixime 18 (17.31)
Macrolides 57 (54.81)
Azithromycin 55 (52.88)
Erythromycin 1 (0.96)
Clindamycin 1 (0.96)
Penicillins 26 (25.00)
Piperacillin tazobactam 14 (13.46)
Amoxicillin clavulanic acid 12 (11.54)
Quinolones 11 (10.58)
Moxifloxacin 9 (8.65)
Levofloxacin 2 (1.92)
Ciprofloxacin 1 (0.96)
Imidazoles 10 (9.62)
Metronidazole 10 (9.62)
Carbapenems 4 (3.85)
Meropenem 4 (3.85)
THIS IS A COCKTAIL THAT IS VERY DANGEROUS TO HEART MITOCHONDRIA-JORMA JYRKKANEN COMMENT
DISCUSSION

The prevalence of use of antibiotics was 98.1%. About 71.15% patients were treated with two or more antibiotics. The mean number of antibiotics used per patient was 1.86. The mean duration of antibiotics use was 6.33 days. Seventeen different antibiotics were used belonging to 7 different antibiotic classes. The most common class of antibiotics used was cephalosporin at 85 (81.73%) and macrolides at 57 (54.81%).

Even before the COVID-19 pandemic, AMR was projected to become responsible for approximately 10 million deaths worldwide in the coming three decades.7 COVID-19 has undoubtedly affected antibiotic stewardship and has increased antibiotic consumption patterns globally, adding to the already existing global AMR problem. Because of this, the mortality due to AMR is expected to be higher in post COVID era.2 This pandemic has disrupted health delivery systems worldwide. This has increased the overuse of antibiotics, eventually leading to resistant organisms requiring aggressive treatment.8 Thus AMR is a problem of greater concern than COVID-19 which has unfortunately been overshadowed amidst the pandemic.7,9 Increased use of antibiotics is more challenging, especially in the low and middle-income countries (LMIC) due to the inefficiency and inadequacy of health care services.2

The Infectious Diseases Society of America (IDSA) states that only 8% of the COVID-19 patients acquired bacterial/fungal superinfections requiring antibiotics.10 However, a study showed 72% of COVID-19 patients received empirical broad-spectrum antibiotics, even when bacterial coinfection was absent.11 Current World Health Organization guidelines indicate that antibiotics should not be prescribed in mild or moderate COVID-19 cases unless there are pre-existing symptoms of bacterial co-infection. Furthermore, when treating severe cases with an empirical antimicrobial agent, the overall condition of the patient, local bacterial epidemiology, and clinical judgement should be integrated, to ensure judicial antimicrobial usage.12 In COVID-19 patients, antibiotics are used for potential anti-inflammatory, immune-modulating, and potential antiviral properties. But the antiviral mechanism of these agents is doubtful. This widespread antibiotic use is likely to worsen preexisting AMR crisis.13

The influenza pandemic was largely a problem of viral infection complicated by bacterial co-pathogenesis.14 This has been our basis for use of a wide range antibiotics empirically though COVID-19 is primarily a viral pathology and is not conventionally treated with antibiotics.

In a study, 71.00% of the hospitalised COVID-19 patients received antibiotics despite a confirmed bacterial co-infection rate of only 1%.3 Antibiotic was used in 95.00% COVID-19 patients when secondary bacterial infection was only found in 15.00%.4 A systematic review showed the mean rate of antibiotic use was 74.00 %.5 In our study, the prevalence of use of antibiotics was 98.10% which is very high when compared to above studies. In most cases antibiotics use often empirical. Empiric antibiotics were often used for the concern of community-acquired pneumonia (89.00%).15 This showed that antibiotic therapy has been used often empirically in the majority of patients even when very few were proven to have bacterial coinfection.

In our study, 17 different antibiotics belonging to seven antibiotic classes were used. Similar to our study a wide range of antibiotics use was documented in other studies.1,5,10,13,15-18 Many other classes of antibiotics other than above were used in other studies for the management of COVID-19 patients. They are aminoglycosides,1 glycopeptide antibiotic like vancomycin and teicoplanin,10 oxazolidinones like linezolid, tetracycline and cyclic lipopeptides like daptomycin.17 Most of these are newer classes of antibiotics and increased use of these should raise a red flag among concerned clinicians, pharmacists, microbiologists, public health experts, hospitals, local authorities as well as regulatory bodies.

Carbapenem, fluoroquinolones, and aminoglycoside were highly prevalent in ICU patients.1 Similar to this carbapenem was exclusively used for ICU patients in our study. Other commonly used antibiotics among ICU patients were fluoroquinolones, cephalosporin, piperacillin with tazobactam, and macrolides. In general, ICU addmission compromises of a very sick patient with superadded bacterial infection and in regard to COVID-19, it comprises of severe COVID-19 infection often requiring ventilatory support. In such conditions, it is common practice to use multiple higher and broad-spectrum antibiotics.

The common antibiotics in use were ceftriaxone (54.00%), vancomycin (48.00%), azithromycin (47.00%), and cefepime (45.00%).10 In our study ceftriaxone (73.08%) and azithromycin (52.88%) were widely used but cefepime was used in 2.88% of patients and vancomycin was not used at all. Higher antibiotics like cefepime and vancomycin should only be used when there is a valid indication, otherwise, it may result in resistant infection which will be very hard to treat.

Ceftriaxone and azithromycin are often the most common antibiotics used in the management of COVID-19 patients.10,13,15,16 Most of the local guidelines as well as some international guidelines advocate for use of these antibiotics based on the epidemiology of local pathogens and resistance patterns. The advantage of the use of these antibiotics is that it covers most of the opportunistic pathogens that could cause secondary infection in COVID-19. But on the other hand, wide and inappropriate use of these antibiotics can lead to with emergence resistance of these common, cheap, and very efficient antibiotics.

Macrolide, specifically azithromycin, was the most common antibiotic used in the clinical management of COVID-19.13 Macrolides, particularly azithromycin, were used in the treatment of more than half of the patients in our study. These drugs are often used to cover atypical organism that have the potential to cause a secondary infection.10,11

Fluoroquinolones were most used, (56.80%), followed by ceftriaxone (39.50%), then azithromycin (29.10%), and carbapenems were only used in two patients.18 Unlike to above study, in our study fluoroquinolones were used less (10.58%) and ceftriaxone and azithromycin was basically used in most patients. But similarity was observed between ours and the above study regarding the use of carbapenems, which was used in 3.85% of patients. Wide use of carbapenem, used in up to 40.10% of patients was also reported.5 carbapenem is often used as a reserved antibiotic for severe infection thus minimal use of these in COVID-19 signifies the presence of good antibiotics stewardship and antibiotic management system among concerned institutions while wide use can signify the opposite.

The most common antibiotic used was third-generation cephalosporin (ceftriaxone) (53.80%), moxifloxacin (29.50%), and doxycycline (25.40%).5 Similar to the above study the most common class of antibiotics used in our study was cephalosporin (81.74%), around 90.00% of which was third-generation cephalosporin namely ceftriaxone (76/85). But unlike the above, Moxifloxacin was used in only 8.65% and doxycycline or other tetracycline group of drugs was not used at all in our study.

A study showed all patients were receiving at least one antibiotic with 31.08% receiving a single antibiotic and 68.91% receiving multiple antibiotics.5 Similar to this study, 98.10% of patients in our study received at least one antibiotic, 28.35% received single antibiotic agents and 71.15% received multiple antibiotics. But the mean number of antibiotics used in the study above was 2.02 which is more when compared to 1.85 in our study. In 34.6%, three antibiotics were given simultaneously while 9.6% received only one antibiotic.16 Unlike the above, in our study three antibiotics were used in only 14.42% and a single antibiotic was used in 28.85%. The use of multiple antibiotics is worrisome as this might represent unchecked use of antibiotics which will contribute to the worldwide problem of AMR.

In our study, patients with comorbidity were found to have received multiple antibiotics (72.90%). Around 74.00% of patients with diabetes were on multiple antibiotics. Similar findings were documented in another study.5 This might be due to COVID-19 patients with comorbidities like diabetes, airway diseases, hypertension being at greater risk of developing secondary bacterial infection.19 After predicting the risk of secondary infection, multiple antibiotics were used empirically in those patients.

Overall, patients presenting with severe disease received more antibiotics.5 This is also true for our study. COVID-19 patients with co-morbidities and severe COVID-19 are the two most vulnerable groups of patients, thus multiple antibiotics have been found to be used liberally in these patients. These situations can be dealt with systematically by establishing standard antibiotic prescribing guidelines considering local pathogens and sensitivity patterns to antibiotics. This could be further reinforced by appropriate clinical knowledge, laboratory facilities, and surveillance systems.

In our study the mean duration of antibiotics treatment was 6.33 days which is nearly half when compared to 12.71 days with a range from 3 days to 23 days.16 Similar result was found in another study.18 Both of these, decreased and extended duration of antibiotic treatment might represent inappropriate and improper use of antibiotics regimen. Because both, underuse and overuse of antibiotics can result in the emergence of resistance.

Our study is a single centred study and has a small sample size. Therefore, our findings may not be generalizable to other settings.
Go to:
CONCLUSIONS

The prevalence of use of antibiotics among hospitalised COVID-19 patients was found to be higher when compared to other studies conducted in similar settings. Potential bacterial co-infection has been the basis for the use of antibiotics in the management of COVID-19 patients. The rate and number of antibiotics used for mild to moderate disease were also high. The common class of antibiotics used are cephalosporin and macrolides namely ceftriaxone and azithromycin. Higher class antibiotics were mostly used in the management of severe disease in ICU and with ventilator support. However, judicial use of antibiotics among COVID-19 patients with variable severity especially among those admitted in ICU and on ventilatory support could be promoted in order to reduce AMR during this COVID-19 pandemic. Robust antibiotic stewardship programs and surveillance systems should be implemented.
Go to:
ACKNOWLEDGMENTS

The authors would like to acknowledge KIST Medical College and Teaching Hospital for their support.
Go to:
Conflict of Interest

None.
Go to:
REFERENCES

  1. Zeshan B, Karobari MI, Afzal N, Siddiq A, Basha S, Basheer SN, et al. The Usage of Antibiotics by COVID-19 Patients with Comorbidities: The Risk of Increased Antimicrobial Resistance. Antibiotics (Basel). 2021 Dec 29;11(1):35. doi: 10.3390/antibiotics11010035. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  2. Rizvi SG, Ahammad SZ. COVID-19 and antimicrobial resistance: A cross-study. Sci Total Environ. 2022 Feb 10;807(Pt 2):150873. doi: 10.1016/j.scitotenv.2021.150873. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  3. Chen N, Zhou M, Dong X, Qu J, Gong F, Han Y, et al. Epidemiological and clinical characteristics of 99 cases of 2019 novel coronavirus pneumonia in Wuhan, China: a descriptive study. Lancet. 2020 Feb 15;395(10223):507–13. doi: 10.1016/S0140-6736(20)30211-7. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  4. Zhou F, Yu T, Du R, Fan G, Liu Y, Liu Z, et al. Clinical course and risk factors for mortality of adult inpatients with COVID-19 in Wuhan, China: a retrospective cohort study. Lancet. 2020 Mar 28;395(10229):1054–62. doi: 10.1016/S0140-6736(20)30566-3. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  5. Molla MMA, Yeasmin M, Islam MK, Sharif MM, Amin MR, Nafisa T, et al. Antibiotic prescribing patterns at COVID-19 dedicated wards in Bangladesh: findings from a single center study. Infect Prev Pract. 2021 Jun;3(2):100134. doi: 10.1016/j.infpip.2021.100134. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  6. Indian Council of Medical Research. Clinical guidance for management of adult COVID-19 patients [Internet]. New Delhi (IN): Indian Council of Medical Research; 2022. Jan 14, [2022 Jan 14; ]. [2022 Feb 20; ]. https://www.icmr.gov.in/ctechdocad.html Available from: [Google Scholar]
  7. World Health Organization. Antimicrobial resistance [Internet]. Geneva (CH): World Health Organization.; 2021. Nov 17, [2022 Feb 20; ]. https://www.who.int/news-room/fact-sheets/detail/antimicrobial-resistance#cms Available from: [Google Scholar]
  8. Barocas JA, Savinkina A, Lodi S, Epstein RL, Bouton TC, Sperring H, et al. Projected long-term impact of the COVID-19 pandemic on hepatitis C outcomes in the United States: a modelling study. Clin Infect Dis. 2021 Sep 9;:ciab779. doi: 10.1093/cid/ciab779. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  9. Lucien MAB, Canarie MF, Kilgore PE, Jean-Denis G, Fenelon N, Pierre M, et al. Antibiotics and antimicrobial resistance in the COVID-19 era: Perspective from resource-limited settings. Int J Infect Dis. 2021 Mar;104:250–4. doi: 10.1016/j.ijid.2020.12.087. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  10. Neto AGM, Lo KB, Wattoo A, Salacup G, Pelayo J, DeJoy R, et al. Bacterial infections and patterns of antibiotic use in patients with COVID-19. J Med Virol. 2021 Mar;93(3):1489–95. doi: 10.1002/jmv.26441. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  11. Rawson TM, Moore LSP, Zhu N, Ranganathan N, Skolimowska K, Gilchrist M, et al. Bacterial and fungal coinfection in individuals with Coronavirus: A rapid review to support COVID-19 antimicrobial prescribing. Clin Infect Dis. 2020 Dec 3;71(9):2459–68. doi: 10.1093/cid/ciaa530. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  12. Varghese GM, John R, Manesh A, Karthik R, Abraham OC. Clinical management of COVID-19. Indian J Med Res. 2020 May;151(5):401–10. doi: 10.4103/ijmr.IJMR_957_20. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  13. Yacouba A, Olowo-Okere A, Yunusa I. Repurposing of antibiotics for clinical management of COVID-19: a narrative review. Ann Clin Microbiol Antimicrob. 2021 May 21;20(1):37. doi: 10.1186/s12941-021-00444-9. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  14. Morens DM, Taubenberger JK, Fauci AS. Predominant role of bacterial pneumonia as a cause of death in pandemic influenza: implications for pandemic influenza preparedness. J Infect Dis. 2008 Oct 1;198(7):962–70. doi: 10.1086/591708. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  15. Wei W, Ortwine JK, Mang NS, Joseph C, Hall BC, Prokesch BC. Limited Role for Antibiotics in COVID-19: Scarce evidence of bacterial coinfection. [2022 Feb 20; ];medRxiv [Preprint]. 2020 Jun 16; doi: 10.1101/2020.06.16.20133181. https://www.medrxiv.org/content/10.1101/2020.06.16.20133181v1 Available from: [CrossRef] [Google Scholar]
  16. Mustafa L, Tolaj I, Baftiu N, Fejza H. Use of antibiotics in COVID-19 ICU patients. J Infect Dev Ctries. 2021 Apr 30;15(4):501–5. doi: 10.3855/jidc.14404. [PubMed] [CrossRef] [Google Scholar]
  17. Grau S, Echeverria-Esnal D, Gomez-Zorrilla S, Navarrete-Rouco ME, Masclans JR, Espona M, et al. Evolution of antimicrobial consumption during the first wave of COVID-19 pandemic. Antibiotics (Basel). 2021 Jan 29;10(2):132. doi: 10.3390/antibiotics10020132. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  18. Zhu N, Zhang D, Wang W, Li X, Yang B, Song J, et al. A Novel Coronavirus from patients with pneumonia in China, 2019. N Engl J Med. 2020 Feb 20;382(8):727–33. doi: 10.1056/NEJMoa2001017. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
  19. Morgan DJ, Casulli J, Chew C, Connolly E, Lui S, Brand OJ, Rahman R, Jagger C, Hussell T. innate immune cell suppression and the link with secondary lung bacterial pneumonia. Front Immunol. 2018 Dec 14;9:2943. doi: 10.3389/fimmu.2018.02943. [PMC free article] [PubMed] [CrossRef] [Google Scholar]
    THE PROBLEM ARISES FROM THE IMPACT OF A HEAVY DOSE OF ANTIBIOTICS ON THE MITOCHONDRIA AND ALSO THE LOSS OF IMMUNE SYSTEM FUNCTION COINCIDENT WITH LOSS OF MITOCHONDRIAL FUNCTION

Jyrkkanen, Jorma. (2020). Antibiotic induced changes to mitochondria result in potential contributions to carcinogenesis, heart pathologies, other medical conditions and ecosystem risks. Journal of Cardiology and Cardiovascular Medicine. 5. 163-171. 10.29328/journal.jccm.1001104.

In addition to providing energy to support the synthesis of the macromolecules essential for immune cell proliferation, mitochondria also act as signaling organelles, driving activation of immune cells via metabolic intermediates, mitochondrial DNA (mtDNA), and reactive oxygen species (ROS).Mar 22, 2022
Introduction

Immune dysregulation, characterized by an imbalance between a systemic inflammatory response syndrome and a compensatory anti-inflammatory response syndrome, is often observed in critically ill patients [1, 2]. This imbalance between the pro- and anti-inflammatory responses frequently leads to immunoparalysis in critically ill patients, rendering them more susceptible to further infections, and is associated with increased mortality [3]. Currently, no effective treatments are available to restore immune homeostasis and reduce mortality in these patients, largely due to the heterogeneity in patients’ immune status and more importantly the lack of understanding of the underlying cause of such immune dysfunction [2, 4]. Immune response is not a standalone process but is interconnected with other cellular activities, a very important one of which is cellular metabolism. Metabolic pathways and immune response are tightly intertwined both in health and in disease [5]. The link between immune cell function and mitochondrial function is now well recognized and a field known as “immunometabolism” is dedicated to understanding the relationship between immune and metabolic pathways [6,7,8]. Mitochondria play a crucial role in regulating not only the growth, but also the function, of immune cells. In addition to providing energy to support the synthesis of the macromolecules essential for immune cell proliferation, mitochondria also act as signaling organelles, driving activation of immune cells via metabolic intermediates, mitochondrial DNA (mtDNA), and reactive oxygen species (ROS). In addition, mitochondrial dynamics (fusion and fission), biogenesis (synthesis of new mitochondria), and mitophagy (degradation of damaged mitochondria) also play important roles in regulating immune cell functions. Knowledge in immunometabolism in critical illness, in particularly sepsis, opens up a new paradigm in patient care. Potential therapies targeting metabolic pathways, instead of solely immune-related pathways, might be the way to repair cellular function and restore immune homeostasis [4]. The other aspect of immunometabolism—looking at how immune responses influence metabolic pathways—is equally important, but beyond the scope of this review. Interaction between metabolism and immune response at the organ level has been reviewed elsewhere [6].
Mitochondrial Machinery That Mediates and Regulates Immune Responses in Critical Illness

Apart from being the powerhouse of the cell, the mitochondrion has emerged as a signaling hub that shapes and modulates how the immune system responds to infection or trauma. Mitochondrial dysfunction is evident in leukocytes from critically ill patients, and is believed to be the underlying cause of immunoparalysis and may account for the development of organ dysfunction [7,8,9]. Early recovery of mitochondrial function correlates with improved recovery in critically ill patients [10].
Metabolic Reprogramming

The immune-regulating mitochondrial machinery is a complex network involving many pathways and mechanisms that diverge and converge at various levels. Metabolic reprogramming is one mechanism that has been well studied in both innate and adaptive immune cells. Immune cells at different activation states (quiescent vs. activated), or with different functions (pro-inflammatory vs. anti-inflammatory), and different cell types (granulocytes, macrophages, dendritic cells, T- and B-lymphocytes), make use of different metabolic pathways (e.g., glycolysis, oxidative phosphorylation, fatty acid metabolism) to produce ATP [11]. The choice of different metabolic pathways, supports the energy demand of cells at different activation state. For example, upon infection or stimulation, immune cells become activated and produce cytokines and hence tend to favor glycolysis over oxidative phosphorylation for fast turnaround of ATP. Although the same amount of starting material, such as glucose, is used, oxidative phosphorylation generates 18 times more ATP than glycolysis, although is a lot slower. On the other hand, the choice of metabolic pathway determines the fate of the immune cells, i.e., naïve or memory, effector or regulatory, etc. However, the environment that the cells are in in the first place, triggers the changes in the metabolic pathways. The overall trend is that neutrophils, inflammatory macrophages (M1 macrophages), activated effector T cells, and dendritic cells rely more on aerobic glycolysis, whereas alternatively polarized macrophages (M2 macrophages), regulatory T cells (Tregs), and memory T cells prefer oxidative phosphorylation and fatty acid oxidation for energy production [8, 11, 12]. Metabolic reprogramming serves an important role in catering for the immune cells’ energy demand at different phases of their activation and proliferation. However, imbalance across the metabolic pathways could have serious pathological impact. One example may be the hyperlactatemia often seen in critically ill patients. Increased aerobic glycolysis in the activated immune cells during the initial hyper- inflammatory response is believed to contribute to the increase in blood lactate levels in sepsis [13, 14].
Mitochondrial ROS and mtDNA

Metabolic reprogramming sets the scene for the immune response, which is then subjected to many more modifications and regulations by factors that are directly or indirectly related to mitochondrial metabolism. Two important mitochondria-related immune regulators that have been well studied are mitochondrial ROS and mtDNA. Mitochondrial ROS are produced in healthy mitochondria, as a by-product of oxidative phosphorylation. At low dose, mitochondrial ROS serve important signaling functions, especially in the innate immune response. They are known to mediate NLRP3 inflammasome activation, leading to production of the pro-inflammatory cytokines, interleukin (IL)-1β and IL-18 [8, 15]. Mitochondrial ROS also induce a type-I interferon (IFN) response via mitochondrial antiviral-signaling (MAVS) and the IFN regulatory factor 3 (IRF3) pathway [16]. However, the level of mitochondrial ROS needs to be tightly regulated by the antioxidant system. Excessive mitochondrial ROS can cause oxidative damage to proteins/enzymes involved in oxidative phosphorylation and create mutations in mtDNA, contributing to the immune dysregulations as seen in critical illness [17]. Like mitochon-drial ROS, mtDNA also plays an important role in innate immunity [12]. In healthy cells, mtDNA is located in the matrix of mitochondria, encoding 13 proteins, all of which are components of oxidative phosphorylation. mtDNA is released to the cytosol upon mitochondrial dysfunction which involves changes to the integrity or permeability of the mitochondrial membrane. mtDNA, released into the cytosol, can activate the NLRP3 inflammasome with release of IL-1β and IL-18. Due to its bacterial origin, cytosolic mtDNA also serves as a damage-associated molecular pattern (DAMP), which can be recognized by intracellular pattern recognition receptors (PRRs), such as Toll-like receptor 9 (TLR9), and initiate the nuclear factor-kappa B (NF-κB)-dependent pro-inflammatory signaling pathway. In addition, cytosolic mtDNA can also be sensed by cyclic GMP-AMP synthase (cGAS) and activate the cGAS/stimulator of IFN genes (cGAS/STING) pathway and its downstream IFN response [18]. mtDNA can also be released into the circulation and cause systemic inflammation. Circulating mtDNA has been associated with mortality in critically ill patients [19].
Succinate and Itaconate

In addition to mitochondrial ROS and mtDNA, metabolites such as succinate and itaconate have also emerged as part of immune-regulating mitochondrial machinery [4, 20]. Both succinate and itaconate are intermediates from the tricarboxylic acid (TCA) cycle with opposite effects on the immune response. The TCA cycle generates nicotinamide adenine dinucleotide (NADH) and flavin adenine dinucleotide (FADH2), providing electrons to fuel oxidative phosphorylation. Succinate accumulation occurs under conditions such as hypoxia or inflammation. It can be released from mitochondria into the cytosol and functions as a signal transducer promoting pro-inflammatory gene expression via hypoxia-inducible factor 1α (HIF-1α) activation. Accumulation and oxidation of succinate by succinate dehydrogenase (SDH) in the mitochondria also leads to increased production of mitochondrial ROS via a process called reverse electron transport. This further enhances the pro- inflammatory effect of succinate. Like ROS, the level of succinate needs to be carefully regulated due to its inflammation aggravating effect. Plasma succinate has been proposed as a predictor of mortality for critically ill patients who are severely injured [21].

Itaconate, which is derived from cis-aconitate of the TCA cycle, is a succinate-regulating factor. It is shown to counteract the pro-inflammatory effect of succinate by inhibiting SDH. Itaconate can also be released into the cytosol and activate transcription factor NF-E2 p45-related factor 2 (Nrf2), a master regulator of antioxidant and anti-inflammatory responses [22]. Recently, itaconate has also been shown to inhibit the inflammatory response in macrophages through activating transcription factor 3 (ATF3).
Mitochondrial Dynamics

The above mentioned immune-regulating mitochondrial factors are centered around the biochemical aspect of mitochondrial biology. Another important aspect of immune-regulating mitochondrial machinery is mitochondrial dynamics, which is to maintain and provide infrastructural support for the immune response. The size and shape of mitochondria undergo constant change through fusion and fission, which is important for maintaining the health and function of mitochondria. First, fusion incorporates newly synthesized mitochondria (from mitochondrial biogenesis) into the current mitochondrial network. Second, fusion also allows for mixing of proteins and/or mtDNA between the existing mitochondria, which on one hand enhances the metabolic capacity of the mitochondria, and on the other enables the damaged proteins and/or mutated mtDNA to be segregated from the healthy ones. Finally, segregation is achieved via fission and the damaged mitochondria can be destroyed through a process known as mitophagy. The proportion of mitochondria with damaged proteins or mutated mtDNA is kept below a critical threshold level through this process to maintain mitochondrial function [23, 24]. In addition to quality control, mitochondrial fusion and fission also participate in immune regulation. In activated T cells, there is an increase in fission, which creates round and fragmented mitochondria with loose cristae, favoring aerobic glycolysis. And in 146 memory T cells, increased fusion generates elongated mitochondria which favors oxidative phosphorylation and fatty acid oxidation [8, 25].
Immunometabolism: The Perfect World Scenario vs. the Critical Illness Scenario

So far, we have presented a list of mitochondrial components that are thought to play important roles in regulating the immune response. Our list is far from complete, but does highlight a few mechanisms that could relate to the development of immune dysregulation in critical illness. Figure 1 illustrates what we think would happen to the immune response when metabolism was in perfect control (the perfect world scenario) and when it became inconsistent and changeable (the critical illness scenario). In the perfect world scenario, the presence of an insult (e.g., infection or a trauma-related stress signal), would trigger metabolic reprogramming, switching from oxidative phosphorylation to glycolysis. This would enable activation of immune cells and production of pro-inflammatory cytokines and other mediators. At the same time, mitochondrial fission would increase to keep up with the metabolic reprogramming. The slightly elevated mitochondrial ROS and succinate in response to initial insult or cytokines would promote the pro-inflammatory response. Once the insult was eliminated, mitochondrial fusion would increase to create fused elongated mitochondria that favor oxidative phosphorylation and fatty acid oxidation. This would allow activation of regulatory immune cells and production of anti-inflammatory cytokines and other mediators. And itaconate would counteract the effect of succinate, activate the Nrf2-mediated antioxidant pathway to dampen down mitochondrial ROS, and activate ATF3 to inhibit the inflammatory response in macrophages. Immune homeostasis would be achieved as a result.
Fig. 1
figure 1

Immunometabolism in the ‘perfect world scenario’ vs. the ‘critical illness scenario’. OXPHOS oxidative phosphorylation, FAO fatty acid oxidation
Full size image

In the critical illness scenario, initial metabolic reprogramming from oxidative phosphorylation to glycolysis would go on for longer than necessary, generating excessive lactate (hyperlactatemia) and pro-inflammatory cytokines and mediators. A disrupted mitochondrial fusion/fission cycle could be to blame, one which could not support the timely switch to oxidative phosphorylation and fatty acid oxidation. The anti-inflammatory response would eventually kick in but by then damage would already have occurred to mitochondria and mtDNA because of excessive production of ROS in response to stress or cytokines. Excessive ROS and released mtDNA would aggravate the pro-inflammatory response, which in turn would trigger a more aggressive anti-inflammatory response to try and salvage the situation. The competition between pro- and anti-inflammatory responses would exhaust the nutrients and lead to shutdown of the whole metabolic system. Cells would either die or go into hibernation to preserve energy [26]. This scenario is an over-simplified version of what might happen in the actual disease setting, without considering the crosstalk between cells and organs and many other factors that are not included here. It is designed to shed light on the interaction between the immune response and metabolism.
Potential of Mitochondria-Targeting Therapy in Critical Care

Our understanding thus far leads us to think that targeting mitochondria could perhaps correct the underlying cause of immune dysfunction in critical illness and lead to better recovery of the patients. The central role of mitochondrial dynamics in supporting and initiating metabolic reprogramming would make it the perfect therapeutic target. To get the fusion/fission cycle going, the mitochondrial network needs to be replenished by newly synthesized mitochondria via biogenesis. Therapies that could potentially boost mitochondrial biogenesis are mitochondrial transplantation, metformin, nitric oxide (NO), and carbon monoxide. Mitochondrial transplantation has been used successfully in pediatric patients with myocardial ischemia–reperfusion injury [27]. Metformin can activate peroxisome proliferator-activated receptor (PPAR)-gamma coactivator-1α (PGC-1α), and Nrf2, the master regulator of mitochondrial biogenesis and antioxidant systems [28]. Premorbid use of metfor-min is associated with lower mortality in sepsis [29]. NO and carbon monoxide can also enhance mitochondrial biogenesis [30,31,32]. Dietary nitrite has been trialed in patients with coronary artery disease (ClinicalTrials.gov Identifier: NCT00069654). Other therapies, such as mitochondria-targeted antioxidant (MitoQ) [33], could also be beneficial in protecting mtDNA and oxidative phosphorylation from oxidative damage. MitoQ has been trialed in people with Parkinson’s disease (ClinicalTrials. gov Identifier: NCT00329056).
Challenges of Applying Mitochondria-Targeting Therapy in Critical Care

There are challenges to overcome before mitochondria-targeting therapy would be possible. First, how do we assess mitochondrial dysfunction in the clinic and identify patients who would benefit from such therapy? A few possible ways could be considered. Non-invasive assessment of mitochondrial oxygen metabolism using a novel device called the COMET monitor was tested on 40 patients during the acute phase of sepsis. This device is based on the protoporphyrin IX-triplet state lifetime technique (PpIX-TSLT) and has been shown to be feasible [33]. This technology is still in its early phase of clinical application but does offer some hope. Another possible biomarker that could potentially be used for assessing mitochondrial dysfunction is plasma mtDNA, but its sensitivity and specificity need further investigation [19, 34, 35]. Furthermore, we could consider using immune response markers as a surrogate markers, one such example could be IFNα inducible protein 27 (IFI27) [36]. If we could overcome the first challenge, the second would be how to deliver mitochondria-targeting therapies to the right organ at the right time.
Conclusion

In this chapter, we have demonstrated the important role of mitochondria in regulating the immune response and proposed a scenario that explains immune–metabolism crosstalk in the context of critical illness. We have highlighted the role of mitochon-drial dynamics in overseeing and supporting metabolic reprogramming during immune cell activation. Mitochondrial ROS can be friend or foe when it comes to immune regulation. Two TCA intermediates—succinate and itaconate—with opposite effects have emerged as important players of the immune-regulating mitochon-drial machinery. Our understanding in immunometabolism could take us to the next era of critical care: mitochondria-targeting therapy.
Availability of data and material

Not applicable.
References

Duggal NA, Snelson C, Shaheen U, Pearce V, Lord JM. Innate and adaptive immune dysregulation in critically ill ICU patients. Sci Rep. 2018;8:10186.

Article

Google Scholar


Surbatovic M, Vojvodic D, Khan W. Immune response in critically ill patients. Mediat Inflamm. 2018;2018:9524315.

Article

Google Scholar


Frazier WJ, Hall MW. Immunoparalysis and adverse outcomes from critical illness. Pediatr Clin N Am. 2008;55:647–68.

Article

Google Scholar


Koutroulis I, Batabyal R, McNamara B, Ledda M, Hoptay C, Freishtat RJ. Sepsis immuno-metabolism: from defining sepsis to understanding how energy production affects immune response. Crit Care Explor. 2019;1:e0061.

Article

Google Scholar


Faas MM, de Vos P. Mitochondrial function in immune cells in health and disease. Biochim Biophys Acta Mol Basis Dis. 2020;1866:165845.

Article

CAS

Google Scholar


Lercher A, Baazim H, Bergthaler A. Systemic immunometabolism: challenges and opportunities. Immunity. 2020;53:496–509.

Article

CAS

Google Scholar


McBride MA, Owen AM, Stothers CL, et al. The metabolic basis of immune dysfunction following sepsis and trauma. Front Immunol. 2020;11:1043.

Article

CAS

Google Scholar


Angajala A, Lim S, Phillips JB, et al. Diverse roles of mitochondria in immune responses: novel insights into immuno-metabolism. Front Immunol. 2018;9:1605.

Article

Google Scholar


Cheng SC, Scicluna BP, Arts RJ, et al. Broad defects in the energy metabolism of leukocytes underlie immunoparalysis in sepsis. Nat Immunol. 2016;17:406–13.

Article

CAS

Google Scholar


Carré JE, Orban JC, Re L, et al. Survival in critical illness is associated with early activation of mitochondrial biogenesis. Am J Respir Crit Care Med. 2010;182:745–51.

Article

Google Scholar


Pearce EL, Pearce EJ. Metabolic pathways in immune cell activation and quiescence. Immunity. 2013;38:633–43.

Article

CAS

Google Scholar


Sack MN. Mitochondrial fidelity and metabolic agility control immune cell fate and function. J Clin Invest. 2018;128:3651–61.

Article

Google Scholar


Haji-Michael PG, Ladrière L, Sener A, Vincent JL, Malaisse WJ. Leukocyte glycolysis and lactate output in animal sepsis and ex vivo human blood. Metabolism. 1999;48:779–85.

Article

CAS

Google Scholar


Gibot S. On the origins of lactate during sepsis. Crit Care. 2012;16:151.

Article

Google Scholar


Zhou R, Yazdi AS, Menu P, Tschopp J. A role for mitochondria in NLRP3 inflammasome activation. Nature. 2011;469:221–5.

Article

CAS

Google Scholar


Agod Z, Fekete T, Budai MM, et al. Regulation of type I interferon responses by mitochondria-derived reactive oxygen species in plasmacytoid dendritic cells. Redox Biol. 2017;13:633–45.

Article

CAS

Google Scholar


Abilés J, de la Cruz AP, Castaño J, et al. Oxidative stress is increased in critically ill patients according to antioxidant vitamins intake, independent of severity: a cohort study. Crit Care. 2006;10:R146.

Article

Google Scholar


Riley JS, Tait SW. Mitochondrial DNA in inflammation and immunity. EMBO Rep. 2020;21:e49799.

Article

CAS

Google Scholar


Harrington JS, Huh JW, Schenck EJ, Nakahira K, Siempos II, Choi AMK. Circulating mitochondrial DNA as predictor of mortality in critically ill patients: a systematic review of clinical studies. Chest. 2019;156:1120–36.

Article

Google Scholar


Murphy MP, O’Neill LAJ. Krebs cycle reimagined: the emerging roles of succinate and itaconate as signal transducers. Cell. 2018;174:780–4.

Article

CAS

Google Scholar


D’Alessandro A, Moore HB, Moore EE, Reisz JA, Wither MJ, Ghasasbyan A, et al. Plasma succinate is a predictor of mortality in critically injured patients. J Trauma Acute Care Surg. 2017;83:491–5.

Article

Google Scholar


Mills EL, Ryan DG, Prag HA, et al. Itaconate is an anti-inflammatory metabolite that activates Nrf2 via alkylation of KEAP1. Nature. 2018;556:113–7.

Article

CAS

Google Scholar


Garbern JC, Lee RT. Mitochondria and metabolic transitions in cardiomyocytes: lessons from development for stem cell-derived cardiomyocytes. Stem Cell Res Ther. 2021;12:177.

Article

Google Scholar


Carelli V, Maresca A, Caporali L, Trifunov S, Zanna C, Rugolo M. Mitochondria: biogenesis and mitophagy balance in segregation and clonal expansion of mitochondrial DNA mutations. Int J Biochem Cell Biol. 2015;63:21–4.

Article

CAS

Google Scholar


Mills EL, Kelly B, O’Neill LAJ. Mitochondria are the powerhouses of immunity. Nat Immunol. 2017;18:488–98.

Article

CAS

Google Scholar


Singer M. The role of mitochondrial dysfunction in sepsis-induced multi-organ failure. Virulence. 2014;5:66–72.

Article

Google Scholar


McCully JD, Cowan DB, Emani SM, Del Nido PJ. Mitochondrial transplantation: from animal models to clinical use in humans. Mitochondrion. 2017;34:127–34.

Article

CAS

Google Scholar


Katila N, Bhurtel S, Park PH, Choi DY. Metformin attenuates rotenone-induced oxidative stress and mitochondrial damage via the AKT/Nrf2 pathway. Neurochem Int. 2021;148:105120.

Article

CAS

Google Scholar


Tan K, Simpson A, Huang S, Tang B, McLean A, Nalos M. The association of premorbid metformin exposure with mortality and organ dysfunction in sepsis: a systematic review and meta-analysis. Crit Care Explor. 2019;1:e0009.

Article

Google Scholar


Nisoli E, Clementi E, Paolucci C, et al. Mitochondrial biogenesis in mammals: the role of endogenous nitric oxide. Science. 2003;299:896–9.

Article

CAS

Google Scholar


Shiva S, Sack MN, Greer JJ, et al. Nitrite augments tolerance to ischemia/reperfusion injury via the modulation of mitochondrial electron transfer. J Exp Med. 2007;204:2089–102.

Article

CAS

Google Scholar


Lancel S, Hassoun SM, Favory R, Decoster B, Motterlini R, Neviere R. Carbon monoxide rescues mice from lethal sepsis by supporting mitochondrial energetic metabolism and activating mitochondrial biogenesis. J Pharmacol Exp Ther. 2009;329:641–8.

Article

CAS

Google Scholar


Lowes DA, Thottakam BM, Webster NR, Murphy MP, Galley HF. The mitochondria-targeted antioxidant MitoQ protects against organ damage in a lipopolysaccharide-peptidoglycan model of sepsis. Free Radic Biol Med. 2008;45:1559–65.

Article

CAS

Google Scholar


Faust HE, Reilly JP, Anderson BJ, et al. Plasma mitochondrial DNA levels are associated with ARDS in trauma and sepsis patients. Chest. 2020;157:67–76.

Article

CAS

Google Scholar


Mao JY, Li DK, Zhang HM, Wang XT, Liu DW. Plasma mitochondrial DNA levels are associated with acute lung injury and mortality in septic patients. BMC Pulm Med. 2021;21:66.

Article

CAS

Google Scholar


Tang BM, Shojaei M, Parnell GP, et al. A novel immune biomarker IFI27 discriminates between influenza and bacteria in patients with suspected respiratory infection. Eur Respir J. 2017;49:1602098.

Excess Deaths the Humanities Project; Large Global Murder Proof. Evidence Points at Vaccines. Jorma Jyrkkanen

March 21, 2023

2020, 2021,2022 Ed Dowd did Under an organization called the Humanities Project compile a history of excess deaths during and after the pandemic and here is what they found.

Question  Did more all-cause deaths occur during the first months of the coronavirus disease 2019 (COVID-19) pandemic in the United States compared with the same months during previous years?

Findings 2020  In this cohort study, the number of deaths due to any cause increased by approximately 122 000 from March 1 to May 30, 2020, which is 28% higher than the reported number of COVID-19 deaths.

Meaning  Official tallies of deaths due to COVID-19 underestimate the full increase in deaths associated with the pandemic in many states.

Abstract

Importance  Efforts to track the severity and public health impact of coronavirus disease 2019 (COVID-19) in the United States have been hampered by state-level differences in diagnostic test availability, differing strategies for prioritization of individuals for testing, and delays between testing and reporting. Evaluating unexplained increases in deaths due to all causes or attributed to nonspecific outcomes, such as pneumonia and influenza, can provide a more complete picture of the burden of COVID-19.

Objective  To estimate the burden of all deaths related to COVID-19 in the United States from March to May 2020.

Design, Setting, and Population  This observational study evaluated the numbers of US deaths from any cause and deaths from pneumonia, influenza, and/or COVID-19 from March 1 through May 30, 2020, using public data of the entire US population from the National Center for Health Statistics (NCHS). These numbers were compared with those from the same period of previous years. All data analyzed were accessed on June 12, 2020.

Main Outcomes and Measures  Increases in weekly deaths due to any cause or deaths due to pneumonia/influenza/COVID-19 above a baseline, which was adjusted for time of year, influenza activity, and reporting delays. These estimates were compared with reported deaths attributed to COVID-19 and with testing data.

Results  There were approximately 781 000 total deaths in the United States from March 1 to May 30, 2020, representing 122 300 (95% prediction interval, 116 800-127 000) more deaths than would typically be expected at that time of year. There were 95 235 reported deaths officially attributed to COVID-19 from March 1 to May 30, 2020. The number of excess all-cause deaths was 28% higher than the official tally of COVID-19–reported deaths during that period. In several states, these deaths occurred before increases in the availability of COVID-19 diagnostic tests and were not counted in official COVID-19 death records. There was substantial variability between states in the difference between official COVID-19 deaths and the estimated burden of excess deaths.


Conclusions and Relevance  Excess deaths provide an estimate of the full COVID-19 burden and indicate that official tallies likely undercount deaths due to the virus. The mortality burden and the completeness of the tallies vary markedly between states.

Discussion

Monitoring excess deaths has been used as a method for tracking influenza mortality for more than a century. Herein, we used a similar strategy to capture COVID-19 deaths that had not been attributed specifically to the pandemic coronavirus. Monitoring trends in broad mortality outcomes, like changes in all-cause and pneumonia/influenza/COVID-19 mortality, provides a window into the magnitude of the mortality burden missed in official tallies of COVID-19 deaths. Given the variability in testing intensity between states and over time, this type of monitoring provides key information on the severity of the pandemic and the degree to which viral testing might be missing deaths caused by COVID-19. These findings demonstrate that estimates of the death toll of COVID-19 based on excess all-cause mortality may be more reliable than those relying only on reported deaths, particularly in places that lack widespread testing.

Syndromic end points, such as deaths due to pneumonia/influenza/COVID-19, outpatient visits for influenza-like illness, and emergency department visits for fever, can provide a crude but informative measure of the progression of the outbreak.18 These measures themselves can be biased by changes in health-seeking behavior and how conditions are recorded. However, in the absence of widespread and systematic testing for COVID-19, they provide a useful measure of pandemic progression and the impact of interventions.

The gap between reported COVID-19 deaths and excess deaths can be influenced by several factors, including the intensity of testing; guidelines on the recording of deaths that are suspected to be related to COVID-19 but do not have a laboratory confirmation; and the location of death (eg, hospital, nursing home, or unattended death at home). For instance, deaths that occur in nursing homes might be more likely to be recognized as part of an epidemic and correctly recorded as due to COVID-19. As the pandemic has progressed, official statistics have become better aligned with excess mortality estimates, perhaps due to enhanced testing and increased recognition of the clinical features of COVID-19. In New York City, official COVID-19 death counts were revised after careful inspection of death certificates, adding an extra 5048 probable deaths to the 13 831 laboratory-confirmed deaths.19 As a result, the all-cause excess mortality burden from March 11 to May 2, 2020, is only 27% higher than official COVID-19 statistics.19 This aligns well with our estimate of 26% for a similar period in New York City, using a slightly different modeling approach.

Many European countries have experienced sharp increases in all-cause deaths associated with the pandemic. Real-time all-cause mortality data from the EuroMomo project (https://www.euromomo.eu/) demonstrate gaps between the official COVID-19 death toll and excess deaths that echo findings in our study. These gaps are more pronounced in countries that were affected more and earlier by the pandemic and had weak testing. Very limited excess mortality information is available from Asia, Africa, the Middle East, and South America thus far; these data will be important to fully capture the heterogeneity of death rates related to the COVID-19 pandemic across the world. Prior work on the 1918 and 2009 pandemics has shown substantial heterogeneity in mortality burden between countries, in part related to health care.8,20

Humanities Project Excess Deaths USA by Year and Vaccination Status

Horowitz Possible Explanation from Pfizer Databank

https://t.co/Ty6zwCe6J3

https://twitter.com/iluminatibot/status/1673248924948389890

CARDIOLOGIST PREDICTS HUGE MORTALITY FROM VACCINE LINKED MYOCARDITIS https://twitter.com/i/status/1684233024815218688